TECHNOLOGY EXPLAINER
The Blood-Brain Barrier (BBB)
— Getting Past a Wall That Lets Little Through, by Riding a Receptor
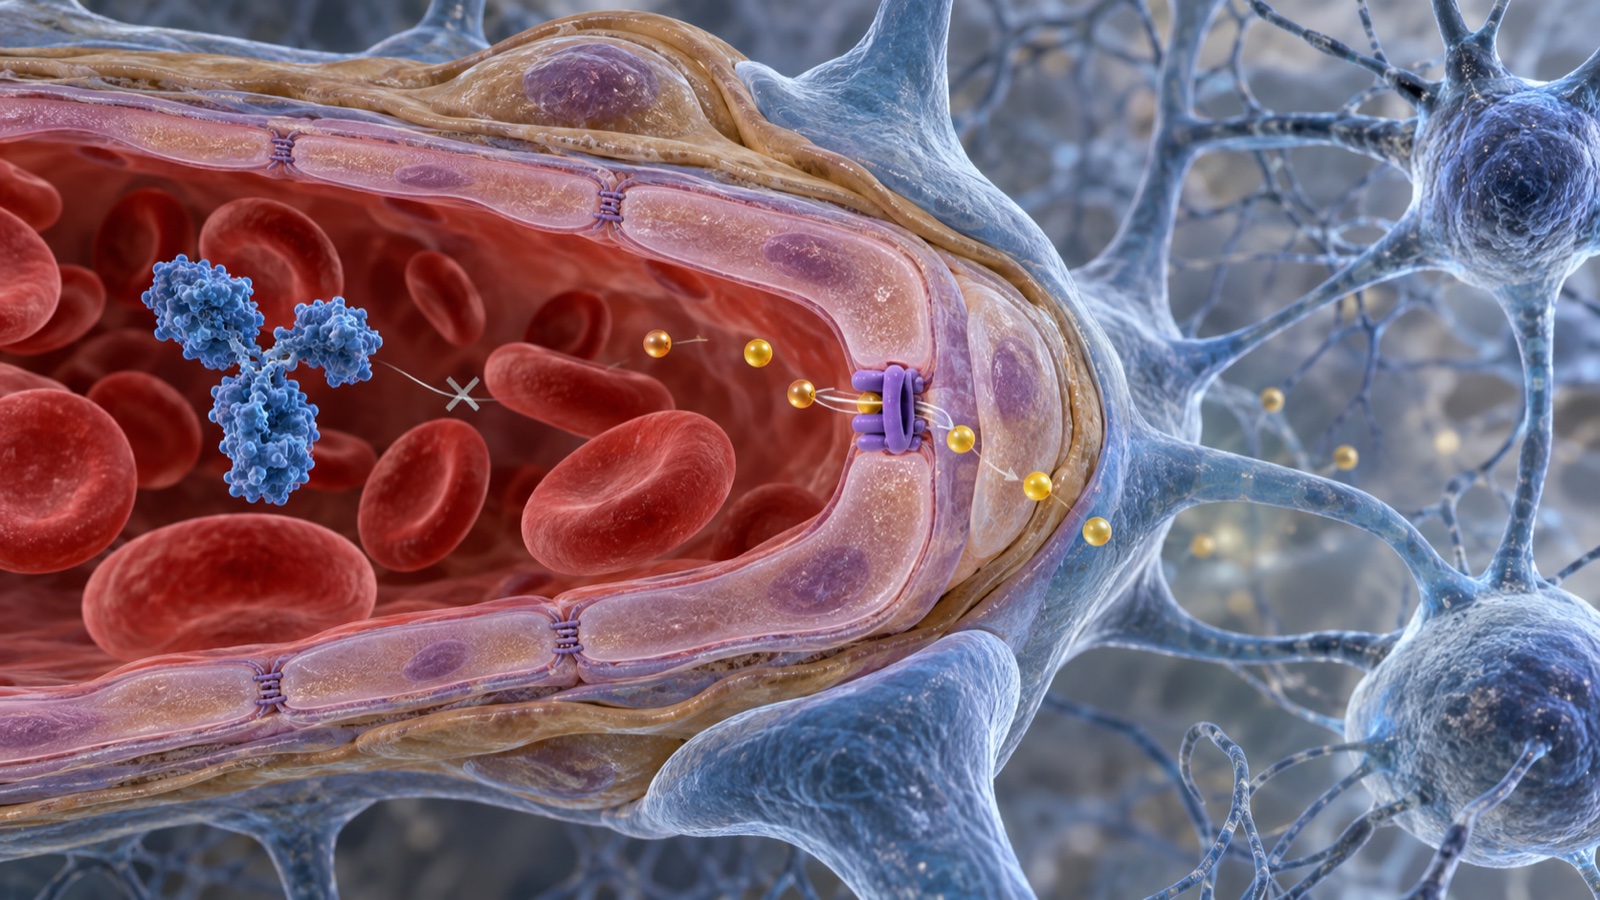
The endothelial cells of the brain's capillaries seal the gaps between them with tight junctions. The design that has reached practical use for getting across is to bind the transferrin receptor and be carried through the cell. In Japan in 2021 and in the United States in 2026, two products that use the same receptor but differ in structure were approved.
- What the blood-brain barrier is (the short version)
- What the wall is made of — tight junctions and the cells around them
- Two kinds of barrier — a physical wall and a transport wall
- Receptor-mediated transcytosis (RMT) as a way through
- Lowering affinity helps more get in — the 2011 paradox
- A materials engineer's view (1): neither adhesion nor adsorption, but "hand over and let go"
- Widening the choice of receptors — choosing by protein abundance
- Two approved products — the same receptor, different structures
- Our calculation: comparing the mass of what is in the vial with the size of the carrier
- A materials engineer's view (2): most of a freeze-dried product is sugar
- Not crossing at all — intrathecal and intraventricular administration
- How it is evaluated — from cell models to the basis for approval
- Open questions, and what has not been confirmed
- Glossary / References / Claim-to-source audit
Sourced = stated in published material (link given)
Our calculation = a value this article derived from the assumptions stated
Not yet confirmed = a research-stage item or plan, or something for which no record has been confirmed
Structural readings and materials- or process-design interpretations are kept apart and marked as Commentary.
This article explains materials and formulation technology. It does not assess the efficacy or safety of any individual drug, does not compare products to rank them, and is not medical advice. The structure, composition and approval details of products are quoted only where they appear in published material from the regulators (the US Food and Drug Administration, FDA, and Japan's PMDA). Results from animal experiments do not necessarily apply to humans.
1. What the blood-brain barrier is (the short version)
- What it is for: Abbott et al. state that "neural signalling within the central nervous system (CNS) requires a highly controlled microenvironment", and that cells at three key interfaces — the blood-brain barrier (BBB), the blood-CSF barrier and the arachnoid barrier — form barriers between the blood and the CNSSourced
- Where it sits: the same paper says that "the BBB at the level of brain microvessel endothelium is the major site of blood-CNS exchange"Sourced
- Why it matters for drug discovery: Yu et al. write that "monoclonal antibodies have therapeutic potential for treating diseases of the central nervous system, but their accumulation in the brain is limited by the blood-brain barrier"Sourced. Abbott et al. conclude that "any programme for drug discovery or delivery, to target or avoid the CNS, needs to consider the special features of the BBB"Sourced
In designs that cross the BBB, what worked was not "grip tightly" but "let go at the right moment". Yu et al. show that an antibody with reduced affinity for the transferrin receptor (TfR) moves into the brain betterSourced. Antibodies that bind TfR with high affinity stay associated with the BBB, whereas lower-affinity variants are released from the BBB into the brain — a regime in which the design rule "the stronger the binding, the better" does not hold (our commentary).
2. What the wall is made of — tight junctions and the cells around them
The paper sets out the structure and function of the BBB as "the physical barrier formed by the endothelial tight junctions" and "the transport barrier resulting from membrane transporters and vesicular mechanisms"Sourced.
It also outlines the roles of the associated cells, "especially the endfeet of astrocytic glial cells, and pericytes and microglia"Sourced.
It adds that the BBB "is subject to short and long-term regulation, which may be disturbed in pathology"Sourced.
In another review, Abbott et al. write that there is great interest in "the association of brain microvessels, astrocytes and neurons to form functional 'neurovascular units'", and that recent studies have highlighted "the importance of brain endothelial cells in this modular organization"Sourced.
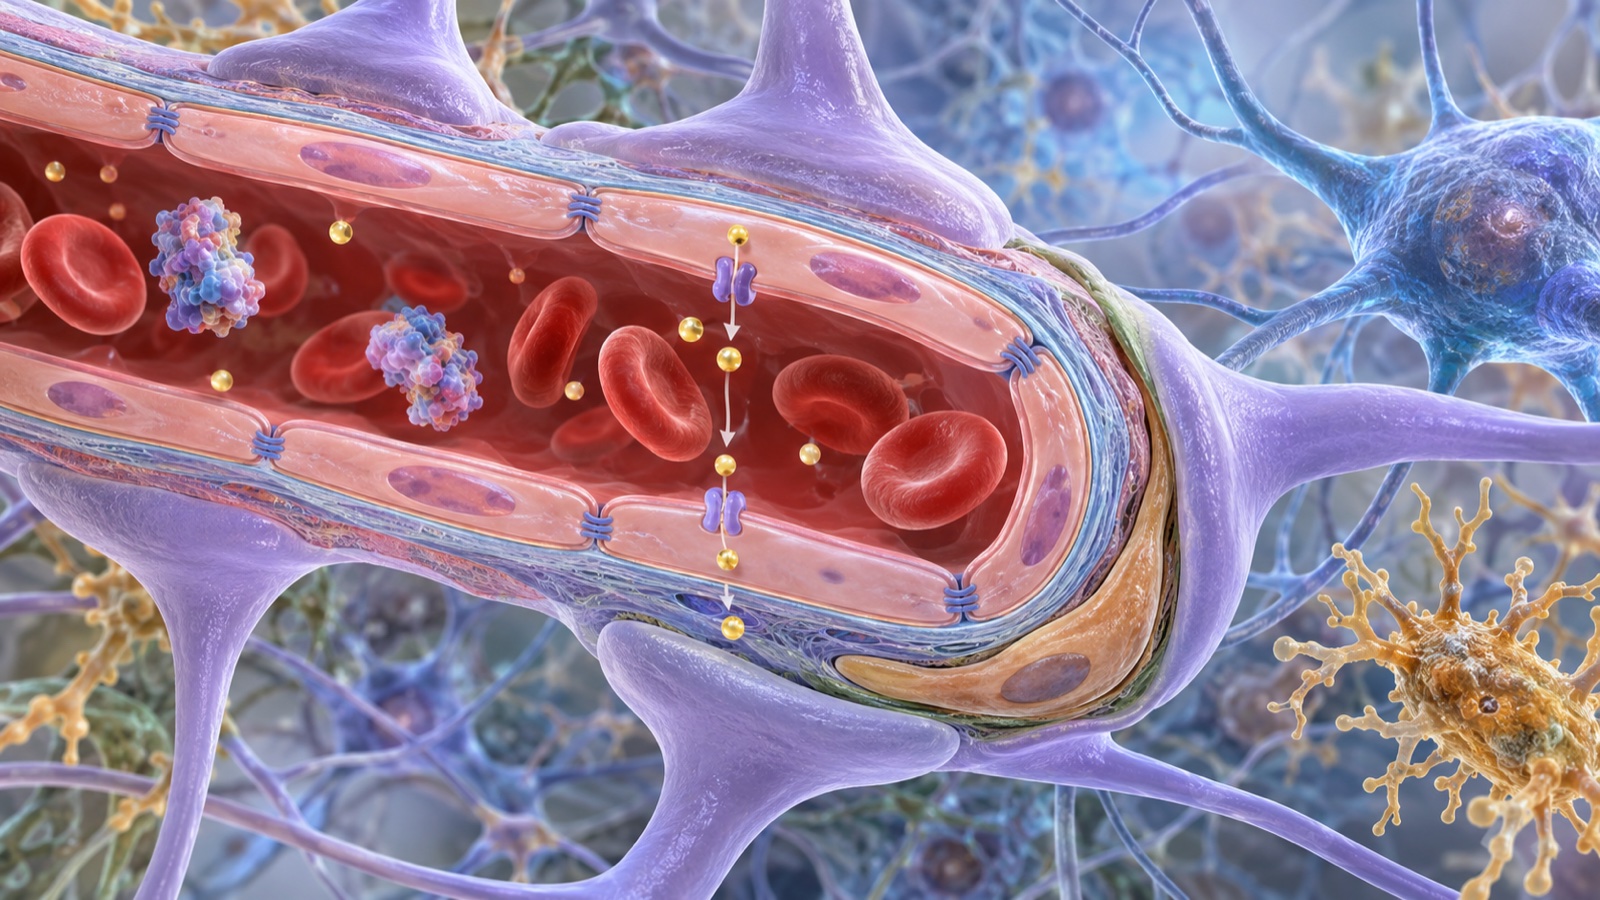
Show the original schematic with sources and figures
Source diagram for Fig. 1 (vector drawing). The division of the structure and the cells involved are from Abbott et al. (2010) [Ref. 1]; the neurovascular-unit concept is from Abbott et al. (2006) [Ref. 2]. The diagram is schematic and does not show the shape, size ratio or arrangement of cells. It is not an actual tissue image.
3. Two kinds of barrier — a physical wall and a transport wall
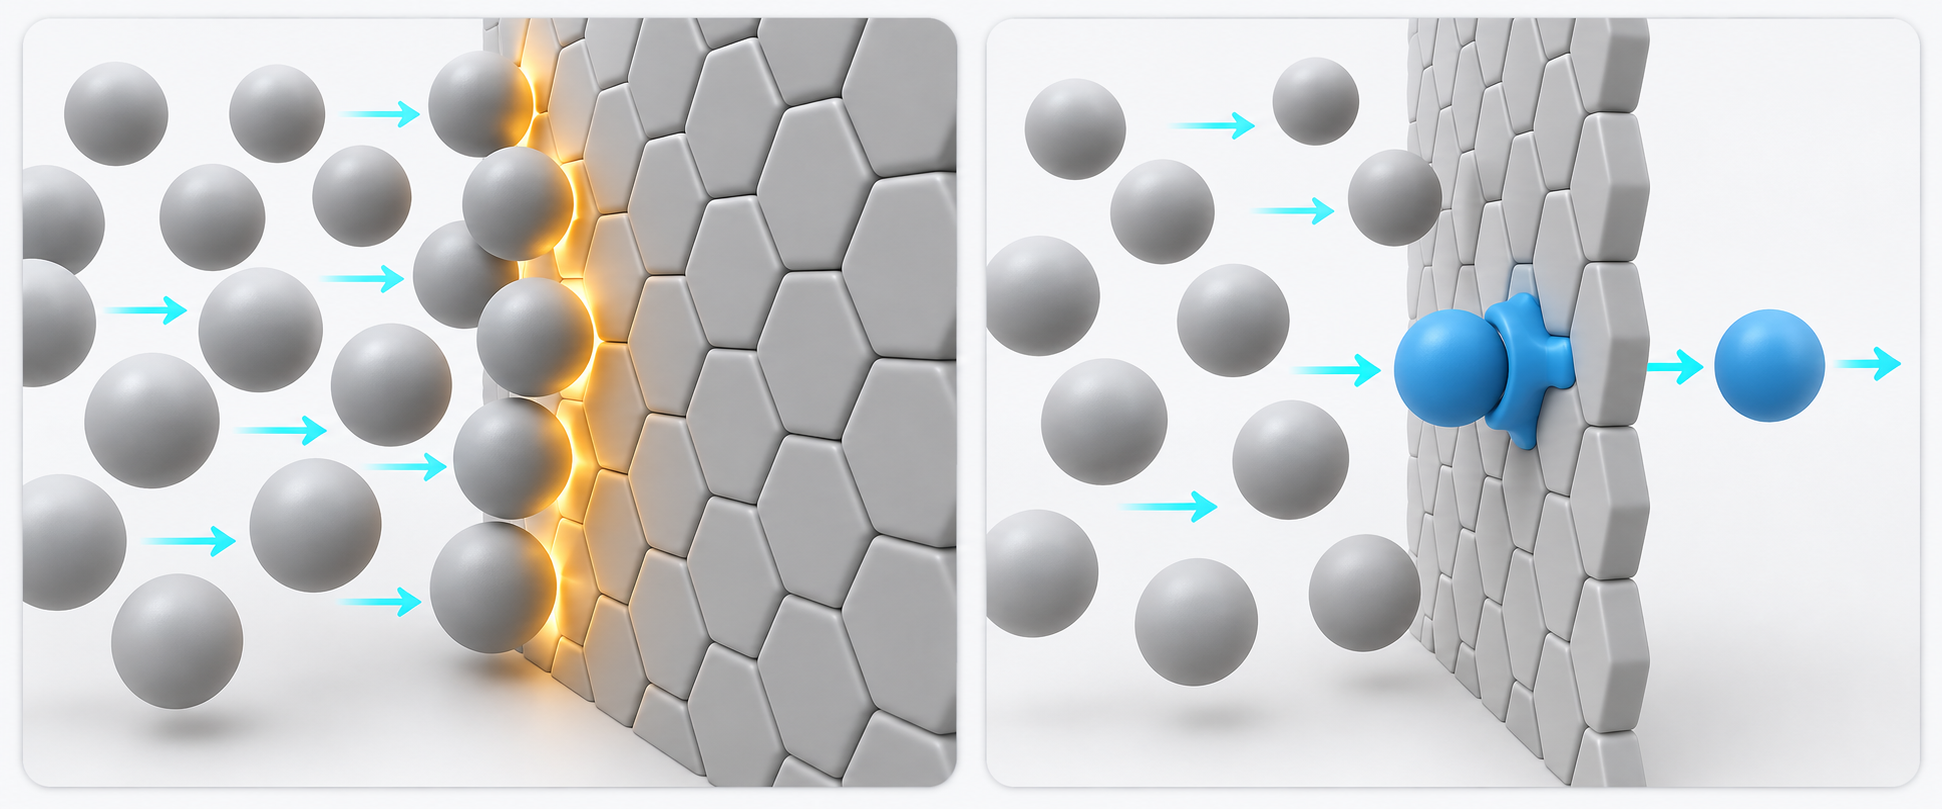
Following Abbott et al., the BBB's "resistance to passage" has two componentsSourced.
| Type of barrier | What it is (per the paper) | How to get past it (this article's reading) |
|---|---|---|
| Physical barrier | Formed by the tight junctions of endothelial cells | The gaps between cells cannot be used. The only way is through the cell |
| Transport barrier | Results from membrane transporters and vesicular mechanisms | Ride along on a transport system that already exists |
The left two columns are Sourced (Abbott et al. 2010 [Ref. 1]). The right column is this article's reading.
"The only way is through the cell" — this is the starting point for drug delivery systems (DDS). And of the "vesicular mechanisms", the one that has actually been used to carry drugs is the receptor-mediated transcytosis of the next chapter.
4. Receptor-mediated transcytosis (RMT) as a way through
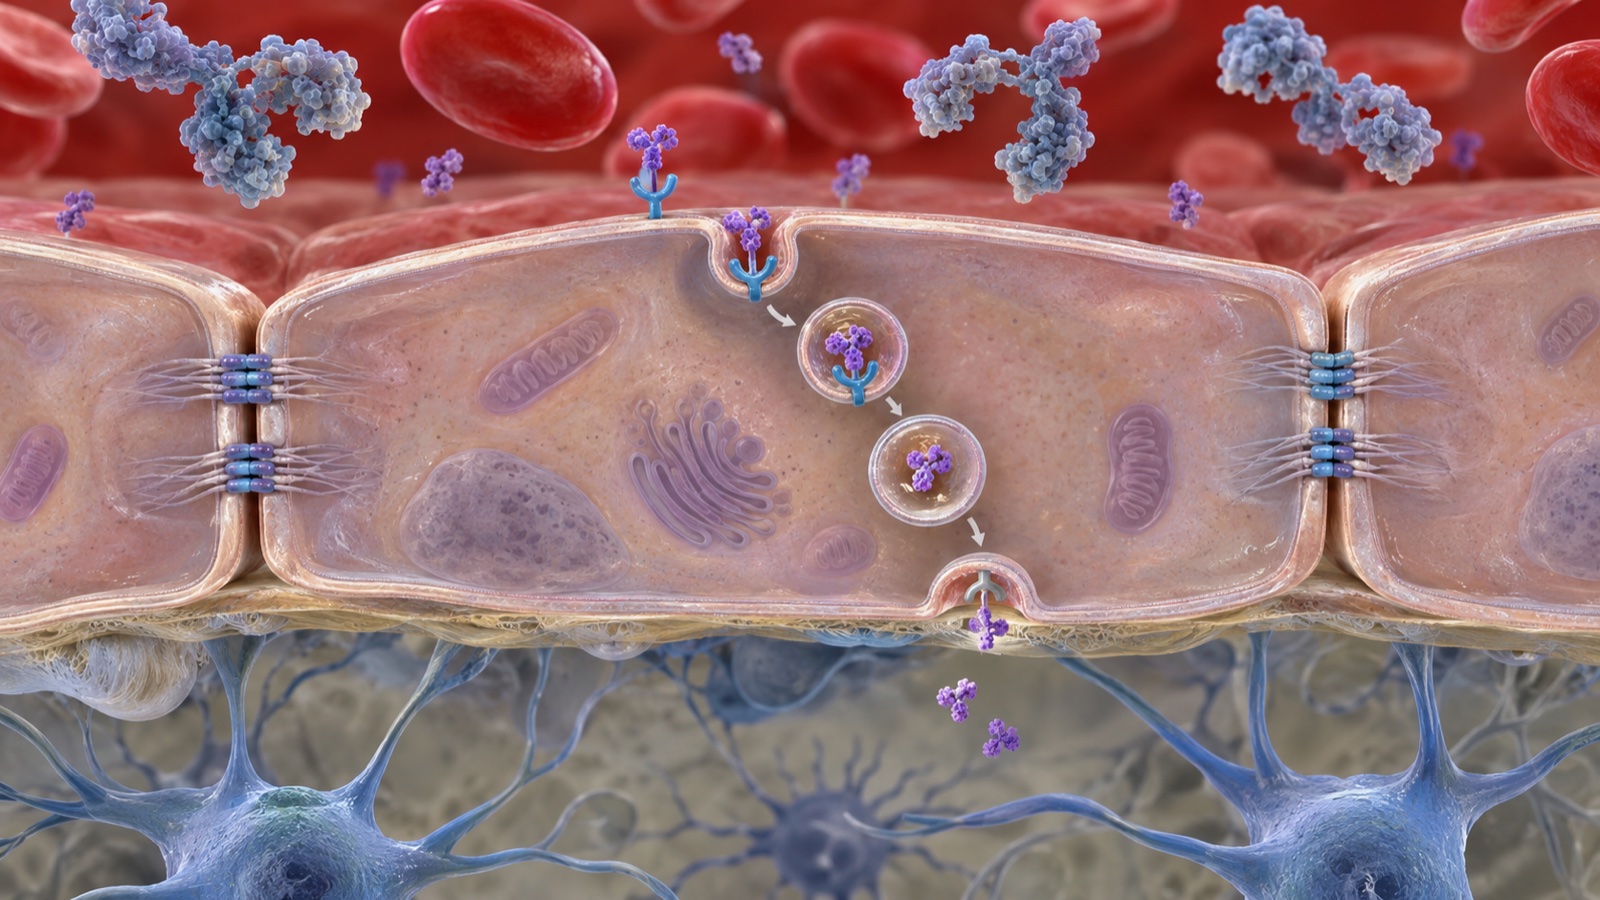
Transcytosis is a mechanism in which a cell takes something up into a vesicle on one side, carries it across the cell and releases it on the other side. If you use something that binds a receptor, you can ride along on it. The labels of approved products describe this.
"The fragment, crystallizable (Fc) component of tividenofusp alfa-eknm binds to the apical domain of the transferrin receptor (TfR) and delivers IDS to peripheral tissues and to the CNS through receptor-mediated transcytosis across the blood-brain barrier" (IDS = iduronate-2-sulfatase, an enzyme)Sourced
The label also says that "since TfR is ubiquitously expressed, it is expected that the interaction of tividenofusp alfa-eknm and TfR will contribute to its uptake into cells in the brain and peripheral tissues"Sourced.
In peripheral tissues and organs, the drug is taken into cells mainly via the cation-independent mannose-6-phosphate receptor and transferrin receptor 1 (TfR), is then carried to lysosomes, and breaks down accumulated glycosaminoglycans (GAG). It also crosses the BBB by TfR-mediated transcytosis and, in cells of the brain parenchyma, is likewise taken up via the cation-independent mannose-6-phosphate receptor and TfR and breaks down accumulated GAGSourced
Both use the transferrin receptor. This receptor is by nature the one that takes up transferrin, the protein that carries iron, into cells; it was not prepared for drugs. Having your cargo carried on a logistics route that is already there — that is the idea of RMT (our commentary).
5. Lowering affinity helps more get in — the 2011 paradox
Once the decision to use RMT is made, designers run into the next question: is stronger binding to the receptor better? The 2011 report of Yu et al. gave an answer that runs against intuitionSourced.
The authors show that "reducing the affinity of an antibody for the transferrin receptor (TfR) enhances receptor-mediated transcytosis of the anti-TfR antibody across the BBB into the mouse brain where it reaches therapeutically relevant concentrations"Sourced
"Anti-TfR antibodies that bind with high affinity to TfR remain associated with the BBB, whereas lower-affinity anti-TfR antibody variants are released from the BBB into the brain and show a broad distribution 24 hours after dosing"Sourced
On the basis of this finding, the paper reports designing a bispecific antibody that binds with low affinity to TfR and with high affinity to the enzyme BACE1. Compared with a monospecific anti-BACE1 antibody, it accumulated more in the mouse brain and led to a greater reduction in brain amyloid-β after a single systemic doseSourced.
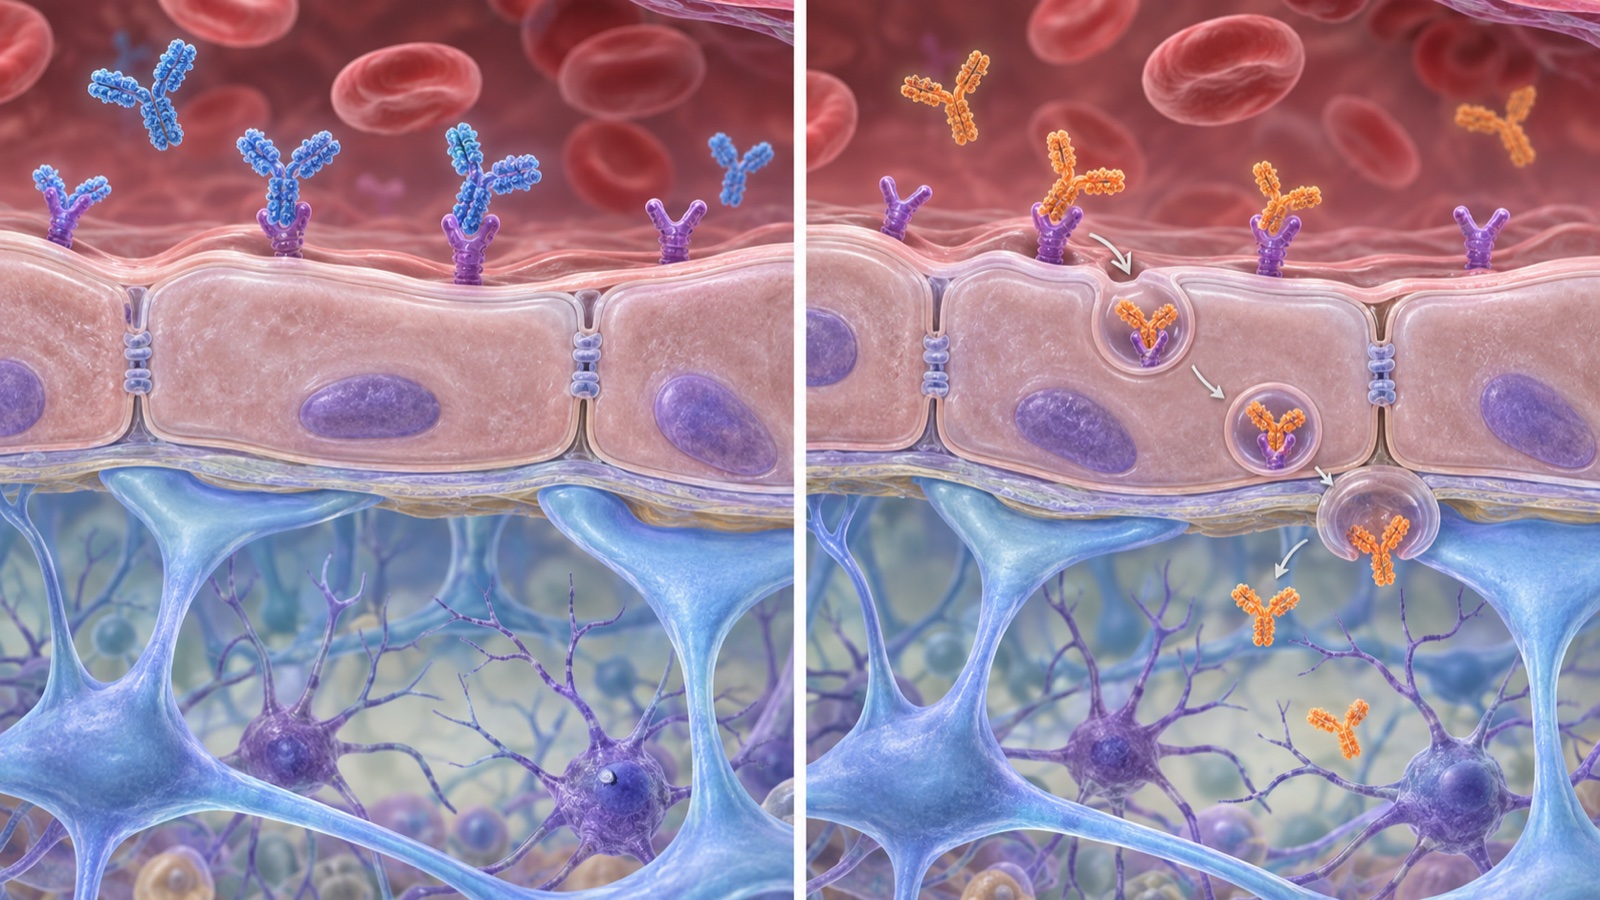
Show the original schematic with sources and figures
Source diagram for Fig. 3 (vector drawing). The statements on the left and right follow the abstract of Yu et al. (2011) [Ref. 3]. The number and placement of dots are schematic and do not show actual distribution or amounts. The sentence in the bottom bar is our summary. These are mouse results, and the same need not happen in humans.
6. A materials engineer's view (1): neither adhesion nor adsorption, but "hand over and let go"
Anyone who works with surface treatments and coupling agents tends to take "how strongly does it bind to its partner" as the performance metric. In RMT across the BBB, however, binding is used only at the entrance, and the molecule must let go at the exit (our commentary). The result of Yu et al. shows exactly this: the high-affinity antibody stays at the BBB, and the low-affinity variant is released into the brainSourced.
In the world of materials, this is close to the design of transfer films and release agents: hold firmly for most of the journey, then release reliably at the intended place. If you raise only the holding force, the film does not peel and there is no product — the same pattern of failure (our commentary).
It is also notable that the design variable boils down to one continuous quantity, "the strength of binding". You vary the antibody sequence to tune affinity step by step and look for the optimum. As a method, it closely resembles what we saw in this series' explainer on lipid nanoparticles: varying the pKa of the ionizable lipid to find the best range (our commentary).
7. Widening the choice of receptors — choosing by protein abundance
Are there usable receptors other than TfR? Zuchero et al. took the approach of searching by comprehensively measuring protein abundanceSourced.
"Using transcriptomic and proteomic profiling, we searched for proteins in mouse brain endothelial cells (BECs) that could potentially be exploited to transport antibodies across the BBB"Sourced
The first result was negative. "Due to their limited protein abundance, neither antibodies against literature-identified targets nor BBB-enriched proteins identified by microarray facilitated significant antibody brain uptake"Sourced.
Then, from proteomic analysis of isolated mouse BECs, they identified multiple highly expressed proteins, including basigin, Glut1 and CD98hc. Antibodies to each of these targets were significantly enriched in the brain after administration in vivo, and in particular antibodies against CD98hc showed robust accumulation in the brain after systemic dosing and a significant pharmacodynamic response, as measured by brain Aβ reductionSourced.
The most suggestive point of this paper is that the reason for failure was "limited protein abundance"Sourced.
However high the affinity, if there are not enough partners, the amount transported will not be large. It is the same story as active-site density in catalysis or functional-group density in adhesion (our commentary). So the search method switched from "search by function" to "search by expression level". Measuring proteins (the proteome) rather than transcripts (a microarray) also fits the mindset of materials analysis, in that it looks at the amount actually present (our commentary).
8. Two approved products — the same receptor, different structures
A design that uses TfR has actually been approved. Two products with different structures have been approved in Japan and the United States for the same disease (mucopolysaccharidosis type II, MPS II, also called Hunter syndrome). Only structure and approval facts are given below. This is not a comparison of efficacy or safety.
| Item | IZCARGO for Intravenous Infusion 10 mg (Japan) | AVLAYAH (United States) |
|---|---|---|
| Generic name | Pabinafusp alfa (genetical recombination) | Tividenofusp alfa-eknm |
| Structure | A recombinant fusion glycoprotein made of a humanized anti-human transferrin receptor monoclonal antibody and human iduronate-2-sulfatase. Two A chains (219 amino acids) and two B chains (975 amino acids); the B chain is antibody heavy chain (γ1) + linker + enzyme | A fusion protein in which the enzyme (IDS) is fused to the N-terminus of an IgG1 Fc |
| Molecular weight | about 300,000 | about 110 kDa |
| Production | Chinese hamster ovary (CHO) cells | Produced in CHO cells by recombinant DNA technology |
| Statement on crossing the BBB | Crosses the BBB by TfR-mediated transcytosis | The Fc binds the apical domain of TfR and crosses the BBB by receptor-mediated transcytosis |
| Dosage form | Freeze-dried formulation (white mass or powder), intravenous infusion | Freeze-dried powder, reconstituted and diluted for intravenous infusion |
| Approval | MPS II. Approval number 30300AMX00260000 (the label's references state approval on 23 March 2021) | BLA 761485, approved on 24 March 2026 (priority review, new active ingredient). Accelerated approval |
The IZCARGO entries are Sourced (PMDA package insert [Ref. 6]); the AVLAYAH entries are Sourced (FDA label [Ref. 5]; approval date and review class from Drugs@FDA [Ref. 7]). The scope of indications, dosage, clinical results and safety differ by product and are not compared in this article. BLA = Biologics License Application.
The label states: "This indication is approved under accelerated approval based on the reduction of cerebrospinal fluid heparan sulfate. Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s)"Sourced.
The study it rests on (Trial 1, NCT04251026) was a phase 1/2 multi-center, multi-cohort, single-arm, open-label trial in 47 pediatric patients. For the 44 patients with measurements at Week 24, the mean percent reduction in cerebrospinal fluid heparan sulfate from baseline was 91% (95% CI 89% to 92%)Sourced. Please note that this is a single-arm trial with no control group, and that the evaluation rests on a surrogate marker (a biomarker).
The same receptor and the same enzyme are carried, but the structure of the carrier differs. One uses the whole antibody, the other only the FcSourced. How far to trim the carrying part is thus one of the design choices (our commentary).
9. Our calculation: comparing the mass of what is in the vial with the size of the carrier
IZCARGO for Intravenous Infusion 10 mg (per vial)Sourced
- Active ingredient: pabinafusp alfa 12.5 mg (an overfill, to secure 10 mg as an injectable amount after allowing for losses during preparation)
- Excipients: sodium chloride 2.0 mg / purified sucrose 187.5 mg / sodium dihydrogen phosphate hydrate 5.34 mg / disodium hydrogen phosphate hydrate 5.64 mg / polyoxyethylene (160) polyoxypropylene (30) glycol 0.8125 mg / sodium hydroxide and hydrochloric acid, as needed
AVLAYAH (per vial)Sourced
- Active ingredient: tividenofusp alfa-eknm 150 mg
- Excipients: dibasic sodium phosphate 5 mg / methionine 7.5 mg / monobasic sodium phosphate 7.7 mg / polysorbate 20 3 mg / sodium chloride 14.6 mg / sucrose 300 mg
Converted from the numbers aboveOur calculation.
- Total excipients in IZCARGO: 2.0 + 187.5 + 5.34 + 5.64 + 0.8125 = 201.29 mg (sodium hydroxide and hydrochloric acid are left out because they are "as needed")
- Excipients to active ingredient: 201.29 ÷ 12.5 = about 16 times
- Share of purified sucrose among the excipients: 187.5 ÷ 201.29 = about 93%
- Overfill ratio: 12.5 ÷ 10 = 1.25 times (a 25% overfill)
- Total excipients in AVLAYAH: 5 + 7.5 + 7.7 + 3 + 14.6 + 300 = 337.8 mg. 337.8 ÷ 150 = about 2.3 times
- Share of sucrose among the excipients: 300 ÷ 337.8 = about 89%
- Ratio of carrier sizes: 300,000 ÷ 110,000 = about 2.7 times (IZCARGO's molecular weight is the about 300,000 stated by PMDA; AVLAYAH's is the about 110 kDa stated by the FDA)
Assumptions and limits: these are amounts per vial, not a dose. Ingredients given as "as needed" are not included in the totals. Both molecular weights are approximate figures from the labels and vary with the amount of glycan. These figures are for looking at the composition of the formulations from a materials standpoint; they do not discuss efficacy, safety or dose.
10. A materials engineer's view (2): most of a freeze-dried product is sugar
What catches the eye in the calculation of Chapter 9 is that in both products, about 90% of the excipients is sugarOur calculation. IZCARGO has purified sucrose 187.5 mg; AVLAYAH has sucrose 300 mgSourced.
Both are freeze-dried formulationsSourced. The IZCARGO label describes its appearance as a white mass or powder (freeze-dried formulation) (our translation), and the AVLAYAH label as "a white to off-white lyophilized powder with a cake-like appearance"Sourced.
As the word "cake" itself suggests, this is a porous solid. The sugar is the structural material that forms its framework and at the same time a protective material that shields the protein from the stresses of freezing and drying (our commentary). In this series' explainer on mRNA we covered how sucrose accounts for the largest mass as a cryoprotectant. Even when the dosage form differs, the pattern of sugar as the largest component is the same.
Look also at the amount of surfactant. IZCARGO has polyoxyethylene (160) polyoxypropylene (30) glycol 0.8125 mg, and AVLAYAH has polysorbate 20 3 mgSourced. Both are tiny amounts, from about 1 mg to a few mg. This is the amount used to keep the protein from denaturing and aggregating at interfaces (air–liquid interfaces, container walls), not an amount aimed at wetting or dispersion — the same kind of surfactant, but different aims mean different orders of magnitude (our commentary).
In addition, the IZCARGO label states explicitly that "this product is overfilled so that 10 mg of pabinafusp alfa (genetical recombination) can be secured as an injectable amount from one vial, allowing for losses during preparation" (our translation)Sourced. A 25% overfillOur calculation — the manufacturer has allowed in advance for what remains in the container and what is lost in transfer. For a product that involves transferring a solution, this shows that the design of the container, stopper and needle bears directly on yield (our commentary).
11. Not crossing at all — intrathecal and intraventricular administration
Apart from the efforts to cross the BBB, there is also the method of putting the drug directly inside the wall. Approved products exist for this too. Only the facts about routes of administration are given below.
| Product (generic name) | Kind | Route of administration (per the label) | First US approval |
|---|---|---|---|
| SPINRAZA (nusinersen) | Modified antisense oligonucleotide (2′-MOE, phosphorothioate) | Intrathecal administration | 23 December 2016 (priority review) |
| QALSODY (tofersen) | 20-base antisense oligonucleotide (5-10-5 MOE gapmer) | Intrathecal administration | 25 April 2023 (priority review) |
| BRINEURA (cerliponase alfa) | Recombinant human tripeptidyl peptidase-1 produced in CHO cells (544 amino acids, average 59 kDa) | Intraventricular administration | 27 April 2017 (priority review) |
All Sourced (FDA labels [Refs. 8–10]; approval dates and review classes from Drugs@FDA [Refs. 11–13]). Indications, dosage, clinical results and safety are not covered in this article. Nucleic acid drugs themselves are covered in this series' explainer on nucleic acid therapeutics. MOE = 2′-O-(2-methoxyethyl).
12. How it is evaluated — from cell models to the basis for approval
At which stage of development, and with what, is crossing of the BBB measured? We organize what can be confirmed from published material.
| Stage | What is used | What the sources say |
|---|---|---|
| Cell models | Culture models based on primary cells or immortalized brain endothelial cell lines | Helms et al. say these "have been developed, in order to facilitate in vitro studies of drug transport to the brain and studies of endothelial cell biology and pathophysiology", and review the existing models with a focus on validation against a set of well-established BBB characteristics. They state that "an ideal cell culture model of the blood-brain barrier is yet to be developed" |
| Searching for molecules | Transcriptomic and proteomic profiling of brain endothelial cells | Zuchero et al. identified highly expressed proteins by proteomic analysis of isolated mouse brain endothelial cells and confirmed in vivo that antibodies to them were enriched in the brain |
| Confirmation in animals | Brain distribution after systemic dosing in mice; disease-model animals | Yu et al. evaluated brain distribution 24 hours after dosing. The IZCARGO label records that repeated intravenous dosing in MPS II model mice reduced GAG in the cerebrospinal fluid, brain, serum, heart, liver and spleen |
| Indicators in humans | Biomarkers in cerebrospinal fluid (CSF) | The accelerated approval of AVLAYAH rests on a reduction in CSF heparan sulfate. The label states that "it is not possible to directly quantify intact HS or DS concentrations in human CSF or urine using currently available bioanalytical methods" and that relative concentrations are estimated from an assessment of selected disaccharides after enzymatic digestion. It also states that "differences in bioanalytical methods preclude meaningful comparison" with the results of other clinical studies |
All Sourced (Helms et al. 2016 [Ref. 4], Zuchero et al. 2016 [Ref. 14], Yu et al. 2011 [Ref. 3], PMDA label [Ref. 6], FDA label [Ref. 5]). HS = heparan sulfate; DS = dermatan sulfate.
The sentence in the AVLAYAH label, "it is not possible to directly quantify intact HS or DS concentrations", is one that anyone in materials analysis should not missSourced.
What is measured is specific disaccharides after enzymatic cleavage, and relative concentrations are estimated from them. The label then adds the warning that "differences in bioanalytical methods preclude meaningful comparison" with the results of other clinical studiesSourced.
If the analytical method differs, values for an indicator with the same name cannot be compared. The same happens in measuring the molecular weight of a polymer or quantifying surface functional groups (our commentary). That the approval document itself spells out this limitation is a useful reference when supplying materials to a regulated industry.
13. Open questions, and what has not been confirmed
(1) Accelerated approval is a state of "being verified"
The indication of AVLAYAH is an accelerated approval based on a reduction in CSF heparan sulfate, and the label itself states that "continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s)"SourcedNot yet confirmed.
(2) No approved product using a receptor other than TfR could be confirmed
CD98hc, basigin and Glut1, as shown by Zuchero et al., are all reports in miceSourced. No primary source showing that a human product using any of them has been approved could be confirmed within the scope of this researchNot yet confirmed.
(3) Crossing the BBB with nanoparticles is not covered in this article
Many studies of delivery to the brain with liposomes and lipid nanoparticles have been reported, but within the scope of this research we could not confirm an approved nanoparticle formulation whose label states that it crosses the BBB and delivers to the brain parenchyma, so none is described here. Nanoparticles themselves are covered in this series' explainers on DDS and targeting and on lipid nanoparticles.
- The BBB is made of a physical barrier from tight junctions and a transport barrier from transporters and vesiclesSourced
- The way through that has reached practical use is receptor-mediated transcytosis. Both approved products use the transferrin receptorSourced
- A mouse report says that lowering receptor affinity improves movement into the brainSourced
- Candidate receptors are now chosen by "expression level". Without sufficient quantity, the amount transported is smallSourced
- With the same receptor and the same enzyme, there are two kinds of carrier: the whole antibody and only the Fc. The ratio of molecular weights is about 2.7 timesOur calculation
- About 90% of the excipients in the freeze-dried products is sugarOur calculation
14. Glossary
- Blood-brain barrier (BBB)
- The wall formed by the endothelium of brain capillaries between blood and brain. It restricts the passage of substances severely.
- Tight junction
- A structure that holds neighboring cells together without gaps. The substance of the physical barrier.
- Endothelial cell
- A cell lining the inside of a blood vessel. In the brain these are the main players of the BBB.
- Astrocyte
- A kind of glial cell in the brain. Its endfeet surround blood vessels.
- Pericyte
- A cell that clings to the outside of a capillary. Involved in BBB function.
- Neurovascular unit
- The concept that brain microvessels, astrocytes and neurons work together.
- Transcytosis
- Transport in which a cell takes something up into a vesicle on one side and releases it on the other.
- RMT
- Receptor-mediated transcytosis. A way to have something pass through a cell by binding a receptor.
- Transferrin receptor (TfR)
- A receptor that takes up the iron-carrying protein. Used as a "vehicle" for crossing the BBB.
- Affinity
- The strength of binding. In crossing the BBB, if it is too strong the molecule does not let go and does not exit into the brain.
- Bispecific antibody
- An antibody that can bind two different partners. Used in designs where one arm carries and the other acts.
- Fc
- The constant-region fragment of an antibody. Involved in interaction with receptors and in how long it stays in the body.
- Fusion protein
- A single molecule made by joining different proteins at the gene level.
- Intrathecal administration
- Administration directly into the space around the spinal cord. The BBB need not be crossed.
- Intraventricular administration
- Administration directly into the ventricles of the brain.
- Accelerated approval
- A US approval pathway based on a surrogate marker. Confirmation in verification trials is a precondition.
- Freeze-dried formulation
- A solid formulation made by freezing and sublimating the water. It is dissolved before use. Sugar provides the framework and the protection.
15. References (primary sources)
- Abbott, N.J., Patabendige, A.A.K., Dolman, D.E.M., Yusof, S.R., Begley, D.J. "Structure and function of the blood-brain barrier", Neurobiology of Disease 37(1), 13–25 (2010). doi:10.1016/j.nbd.2009.07.030 — pubmed.ncbi.nlm.nih.gov
- Abbott, N.J., Rönnbäck, L., Hansson, E. "Astrocyte-endothelial interactions at the blood-brain barrier", Nature Reviews Neuroscience 7(1), 41–53 (2006). doi:10.1038/nrn1824 — pubmed.ncbi.nlm.nih.gov
- Yu, Y.J. et al. "Boosting brain uptake of a therapeutic antibody by reducing its affinity for a transcytosis target", Science Translational Medicine 3(84), 84ra44 (2011). doi:10.1126/scitranslmed.3002230 — pubmed.ncbi.nlm.nih.gov
- Helms, H.C. et al. "In vitro models of the blood-brain barrier: An overview of commonly used brain endothelial cell culture models and guidelines for their use", Journal of Cerebral Blood Flow & Metabolism 36(5), 862–890 (2016). doi:10.1177/0271678X16630991 — pubmed.ncbi.nlm.nih.gov
- FDA / NLM DailyMed "AVLAYAH (tividenofusp alfa-eknm) prescribing information" — dailymed.nlm.nih.gov
- PMDA "IZCARGO for Intravenous Infusion 10 mg, package insert" (in Japanese; JCR Pharmaceuticals, approval number 30300AMX00260000) (PDF) — pmda.go.jp
- FDA Drugs@FDA "BLA 761485 AVLAYAH", approval history — accessdata.fda.gov
- FDA / NLM DailyMed "SPINRAZA (nusinersen) prescribing information" — dailymed.nlm.nih.gov
- FDA / NLM DailyMed "QALSODY (tofersen) prescribing information" — dailymed.nlm.nih.gov
- FDA / NLM DailyMed "BRINEURA (cerliponase alfa) prescribing information" — dailymed.nlm.nih.gov
- FDA Drugs@FDA "NDA 209531 SPINRAZA", approval history — accessdata.fda.gov
- FDA Drugs@FDA "NDA 215887 QALSODY", approval history — accessdata.fda.gov
- FDA Drugs@FDA "BLA 761052 BRINEURA", approval history — accessdata.fda.gov
- Zuchero, Y.J.Y. et al. "Discovery of Novel Blood-Brain Barrier Targets to Enhance Brain Uptake of Therapeutic Antibodies", Neuron 89(1), 70–82 (2016). doi:10.1016/j.neuron.2015.11.024 — pubmed.ncbi.nlm.nih.gov
- ClinicalTrials.gov "NCT04251026: A Study of Tividenofusp Alfa (DNL310) in Pediatric Participants With Hunter Syndrome" — clinicaltrials.gov
16. Claim-to-source audit
| Claim in the text | Basis | Class |
|---|---|---|
| That neural signalling in the CNS requires a highly controlled microenvironment. That there are three interfaces between blood and CNS: the blood-brain barrier, the blood-CSF barrier and the arachnoid barrier. That the BBB at the level of brain microvessel endothelium is the major site of blood-CNS exchange. The distinction between the physical barrier formed by endothelial tight junctions and the transport barrier from membrane transporters and vesicular mechanisms. The involvement of astrocyte endfeet, pericytes and microglia. That the BBB is subject to short and long-term regulation that may be disturbed in pathology. That any programme for drug discovery or delivery, to target or avoid the CNS, needs to consider the special features of the BBB | Abstract of Abbott et al. (2010) Reference 1 https://pubmed.ncbi.nlm.nih.gov/19664713/ | Sourced |
| The concept that brain microvessels, astrocytes and neurons associate to form functional "neurovascular units", and the importance of brain endothelial cells in this modular organization | Abstract of Abbott et al. (2006) Reference 2 https://pubmed.ncbi.nlm.nih.gov/16371949/ | Sourced |
| That monoclonal antibodies have therapeutic potential for CNS diseases but their accumulation in the brain is limited by the BBB. That reducing affinity for TfR enhances receptor-mediated transcytosis of the anti-TfR antibody across the BBB into the mouse brain, reaching therapeutically relevant concentrations. That high-affinity anti-TfR antibodies remain associated with the BBB while lower-affinity variants are released from the BBB into the brain and show a broad distribution 24 hours after dosing. That a bispecific antibody binding TfR with low affinity and BACE1 with high affinity was designed and, compared with a monospecific anti-BACE1 antibody, accumulated more in the mouse brain and led to a greater reduction in brain Aβ after a single systemic dose | Abstract of Yu et al. (2011) Reference 3 https://pubmed.ncbi.nlm.nih.gov/21613623/ | Sourced |
| That culture models based on primary cells or immortalized brain endothelial cell lines have been developed to facilitate in vitro studies of drug transport to the brain and of endothelial cell biology and pathophysiology. That the review covers existing models with a focus on validation against established BBB characteristics. That an ideal cell culture model of the BBB is yet to be developed | Abstract of Helms et al. (2016) Reference 4 https://pubmed.ncbi.nlm.nih.gov/26868179/ | Sourced |
| That tividenofusp alfa-eknm is a fusion protein in which the enzyme IDS is fused to the N-terminus of an IgG1 Fc, produced in CHO cells by recombinant DNA technology, with a molecular weight of about 110 kDa. That one vial contains 150 mg of active ingredient together with dibasic sodium phosphate 5 mg, methionine 7.5 mg, monobasic sodium phosphate 7.7 mg, polysorbate 20 3 mg, sodium chloride 14.6 mg and sucrose 300 mg. That it is a white to off-white lyophilized powder with a cake-like appearance. That the Fc binds the apical domain of TfR and delivers IDS to peripheral tissues and the CNS by receptor-mediated transcytosis across the BBB, and that since TfR is ubiquitously expressed its interaction with the drug is expected to contribute to uptake into cells in the brain and peripheral tissues. That the indication is an accelerated approval based on reduction of CSF heparan sulfate and that continued approval may be contingent on verification and description of clinical benefit in a confirmatory trial. That Trial 1 (NCT04251026) was a phase 1/2 multi-center, multi-cohort, single-arm, open-label trial in 47 pediatric patients and that for the 44 patients with measurements at Week 24 the mean percent reduction in CSF HS was 91% (95% CI 89% to 92%). That intact HS or DS concentrations cannot be quantified directly, that relative concentrations are estimated from selected disaccharides after enzymatic digestion, and that differences in bioanalytical methods preclude meaningful comparison with the results of other clinical studies | FDA AVLAYAH prescribing information Reference 5 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=014d92c1-b643-4680-8ca6-f0b3307da915 | Sourced |
| That pabinafusp alfa is a recombinant fusion glycoprotein of a humanized anti-human transferrin receptor monoclonal antibody and human iduronate-2-sulfatase (molecular weight about 300,000), produced in CHO cells. That it consists of two A chains of 219 amino acids and two B chains of 975 amino acids, the B chain being antibody heavy chain (γ1), linker and enzyme. That in the periphery it is taken up via the cation-independent mannose-6-phosphate receptor and TfR, and that it crosses the BBB by TfR-mediated transcytosis and is taken up by cells of the brain parenchyma. That repeated intravenous dosing in MPS II model mice reduced GAG in CSF, brain, serum, heart, liver and spleen. That the indication is MPS II. The composition per vial (active ingredient 12.5 mg, sodium chloride 2.0 mg, purified sucrose 187.5 mg, sodium dihydrogen phosphate hydrate 5.34 mg, disodium hydrogen phosphate hydrate 5.64 mg, polyoxyethylene (160) polyoxypropylene (30) glycol 0.8125 mg, sodium hydroxide and hydrochloric acid as needed). That it is overfilled so that 10 mg can be secured as an injectable amount. That its appearance is a white mass or powder (freeze-dried formulation). That the approval number is 30300AMX00260000 and that the references state approval on 23 March 2021 | PMDA IZCARGO for Intravenous Infusion 10 mg package insert (in Japanese) Reference 6 https://www.pmda.go.jp/PmdaSearch/iyakuDetail/ResultDataSetPDF/530210_3959424D1023_1_03 | Sourced |
| That AVLAYAH (BLA 761485, Denali Therapeutics) was approved on 24 March 2026, with priority review and as a new active ingredient (Type 1) | Drugs@FDA Reference 7 https://www.accessdata.fda.gov/scripts/cder/daf/index.cfm?event=overview.process&ApplNo=761485 | Sourced |
| That nusinersen is an antisense oligonucleotide with 2′-O-(2-methoxyethyl) modification and phosphorothioate linkages, given intrathecally | FDA SPINRAZA prescribing information Reference 8 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=dd70cd5f-b0fc-4ba4-a5ea-89a34778bd94 | Sourced |
| That tofersen is a 20-base 5-10-5 MOE gapmer antisense oligonucleotide, given intrathecally | FDA QALSODY prescribing information Reference 9 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=81356b45-1cb7-4eef-88ea-e44cc18b47c5 | Sourced |
| That cerliponase alfa is a recombinant human tripeptidyl peptidase-1 produced in CHO cells (544 amino acids, average 59 kDa), given intraventricularly | FDA BRINEURA prescribing information Reference 10 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=485ab3c5-0359-4878-872f-2fe1e7df4047 | Sourced |
| That SPINRAZA (NDA 209531) was approved on 23 December 2016 with priority review | Drugs@FDA Reference 11 https://www.accessdata.fda.gov/scripts/cder/daf/index.cfm?event=overview.process&ApplNo=209531 | Sourced |
| That QALSODY (NDA 215887) was approved on 25 April 2023 with priority review | Drugs@FDA Reference 12 https://www.accessdata.fda.gov/scripts/cder/daf/index.cfm?event=overview.process&ApplNo=215887 | Sourced |
| That BRINEURA (BLA 761052) was approved on 27 April 2017 with priority review | Drugs@FDA Reference 13 https://www.accessdata.fda.gov/scripts/cder/daf/index.cfm?event=overview.process&ApplNo=761052 | Sourced |
| That transcriptomic and proteomic profiling was used to search for mouse brain endothelial cell proteins that could be exploited to transport antibodies across the BBB. That, owing to limited protein abundance, neither antibodies against literature-identified targets nor BBB-enriched proteins identified by microarray facilitated significant antibody brain uptake. That proteomic analysis of isolated mouse brain endothelial cells identified highly expressed proteins including basigin, Glut1 and CD98hc, and that antibodies to them were significantly enriched in the brain after administration in vivo. That antibodies against CD98hc showed robust accumulation in brain after systemic dosing and a significant pharmacodynamic response as measured by brain Aβ reduction | Abstract of Zuchero et al. (2016) Reference 14 https://pubmed.ncbi.nlm.nih.gov/26687840/ | Sourced |
| That NCT04251026 is "A Study of Tividenofusp Alfa (DNL310) in Pediatric Participants With Hunter Syndrome" with actual enrollment of 47 | ClinicalTrials.gov Reference 15 https://clinicaltrials.gov/study/NCT04251026 | Sourced |
| IZCARGO total excipients 201.29 mg, excipients to active ingredient about 16 times, purified sucrose about 93% of the excipients, overfill 1.25 times (25%). AVLAYAH total excipients 337.8 mg, excipients to active ingredient about 2.3 times, sucrose about 89% of the excipients. Ratio of carrier molecular weights 300,000 ÷ 110,000 = about 2.7 times | Our calculation. A simple sum and division of the values in the labels. Ingredients given as "as needed" are not included in the totals. These are amounts per vial, not a dose. Molecular weights are approximate and vary with the amount of glycan. It does not discuss efficacy, safety or dose | Our calculation |
| That the accelerated approval of AVLAYAH may depend on the results of confirmatory trials. The approval status of human products that use CD98hc, basigin or Glut1 | The label itself states the dependence on confirmatory trials. No primary source showing approval of a product using CD98hc and the like could be confirmed as of the research for this article (September 2026) | Not yet confirmed |
| Approved nanoparticle formulations whose labels state that they cross the BBB and deliver to the brain parenchyma | Could not be confirmed within the scope of this research, so none is described | Commentary |
| The framing of "the only way is through the cell". The description of RMT as "having your cargo carried on a logistics route that is already there". The likening of affinity design to transfer films and release agents. The reading that receptor searching switched from "search by function" to "search by expression level", and the likening to active-site density and functional-group density. The positioning of sugar as the structural and protective material of freeze-dried products. The reading that the order of magnitude of surfactant amounts differs by purpose. The reading from the overfill that the design of container, stopper and needle bears directly on yield. The observation that values cannot be compared if the analytical method differs. The grouping of approaches to the wall into three | This article's own organization and commentary based on published content; not views expressed by the authors of the papers or the regulators | Commentary |
| Evaluation of the indications, dosage, clinical results and safety of each product, and comparison between products | This article explains materials and formulation technology and does not evaluate or compare efficacy or safety. For approved products, only the structure, composition and approval details stated in published material from the regulators are quoted. The CSF heparan sulfate figures in Chapter 8 are those the FDA label gives for a single-arm trial with no control group, as a surrogate marker | Commentary |
| That the figures combine ImageGen-generated explanatory images with vector drawings, and are distinguished from real objects or measured images | Note by this article | Commentary |
Last updated 26 September 2026. Sources are limited to primary material (FDA-approved prescribing information, Drugs@FDA, PMDA package inserts, ClinicalTrials.gov, and peer-reviewed papers). Because the article includes readings of materials and formulation design, those are marked as Commentary and kept separate from sourced fact. The relationship between affinity and brain uptake, the search for receptors, and the results in disease models are all values from animal experiments, not values in humans. The label states that the indication of AVLAYAH is an accelerated approval based on a surrogate marker and that continued approval may depend on confirmatory trials. Approved products that use a receptor other than TfR, and approved nanoparticle formulations whose labels state that they cross the BBB, could not be confirmed from the primary information published and are not described. This article explains materials and formulation technology; it does not evaluate the efficacy or safety of any treatment, does not compare products, and is not medical advice. All figures are explanatory concept graphics. The figures combine ImageGen-generated explanatory images with vector drawings. The generated images are not photographs of real objects, micrographs or measured data. The original schematics, which contain figures and sources, are kept either as displayed or in a form that can be expanded below the new images.