TECHNOLOGY EXPLAINER
Immune Checkpoint Inhibitors Explained
— One Residue in an Antibody, and the Enzyme in a Subcutaneous Vial
Immune checkpoint inhibitors are drugs that use antibodies to release the brakes on T cells. Seen through a materials lens, two things stand out. One is the design of antibodies in which a single hinge residue or a single glycosylation site has been re-engineered. The other is the move from intravenous infusion to subcutaneous injection, which depends on much higher protein concentrations and on an enzyme, co-formulated in the same vial, that temporarily breaks down hyaluronan.
- What immune checkpoint inhibitors are (the short version)
- Two brakes — CTLA-4 and PD-1
- The design of approved antibodies — IgG1, IgG4 and Fc engineering
- A materials engineer's view (1): one residue and one glycan site change an antibody's character
- Biomarkers — letting a test decide who is eligible
- Combinations — CTLA-4 antibodies, and antibody-drug conjugates (ADCs)
- Subcutaneous formulations — putting hyaluronidase in the same vial
- Our calculation: how many times more concentrated, and how many mL per minute?
- A materials engineer's view (2): a high-concentration protein and an enzyme in one vial
- Approval status (as confirmed from regulators' published materials)
- Glossary / References / Claim-to-source audit
Sourced = stated in published material (link given)
Our calculation = a value this article derived from the assumptions stated
Not yet confirmed = a plan or goal, or something for which no record has been confirmed
Structural readings and materials- or formulation-design interpretations are kept apart and marked as Commentary.
This article explains antibody design and formulation technology. It does not assess the efficacy or safety of any treatment and is not medical advice. It does not recommend any drug or treatment, rank drugs against one another, or argue whether infusion or subcutaneous injection is better. Where administration times and concentrations are given, they are quoted from the prescribing information in order to explain formulation design. Antibodies in general (structure, production in CHO cells, purification) are covered in more detail in our explainer on antibody drugs and ADCs.
1. What immune checkpoint inhibitors are (the short version)
- What they do: the Nobel Foundation awarded the 2018 Nobel Prize in Physiology or Medicine to James P. Allison and Tasuku Honjo for their discovery of cancer therapy by inhibition of negative immune regulation, and said the two showed how different strategies for inhibiting the brakes on the immune system can be used in the treatment of cancerSourced
- What they are made of: every approved product is a monoclonal antibody. The nivolumab label, for example, describes "an IgG4 kappa immunoglobulin that has a calculated molecular mass of 146 kDa" and says it is expressed in a recombinant Chinese Hamster Ovary (CHO) cell lineSourced
- What is changing now: products that were once given only by intravenous infusion now have subcutaneous versions co-formulated with hyaluronidase. The US Food and Drug Administration (FDA) approved the subcutaneous form of atezolizumab on 12 September 2024, nivolumab on 27 December 2024 and pembrolizumab on 19 September 2025Sourced
The materials and formulation focus in this field is shifting from the antibody itself to its concentration and to what shares the vial with it. The intravenous pembrolizumab formulation is 25 mg per mL; the subcutaneous formulation is 395 mg in 2.4 mL, which works out to about 165 mg/mL, roughly 6.6 times as concentratedOur calculation. And the subcutaneous product carries, in the same vial, an enzyme that temporarily breaks down hyaluronan in subcutaneous tissueSourced.
2. Two brakes — CTLA-4 and PD-1
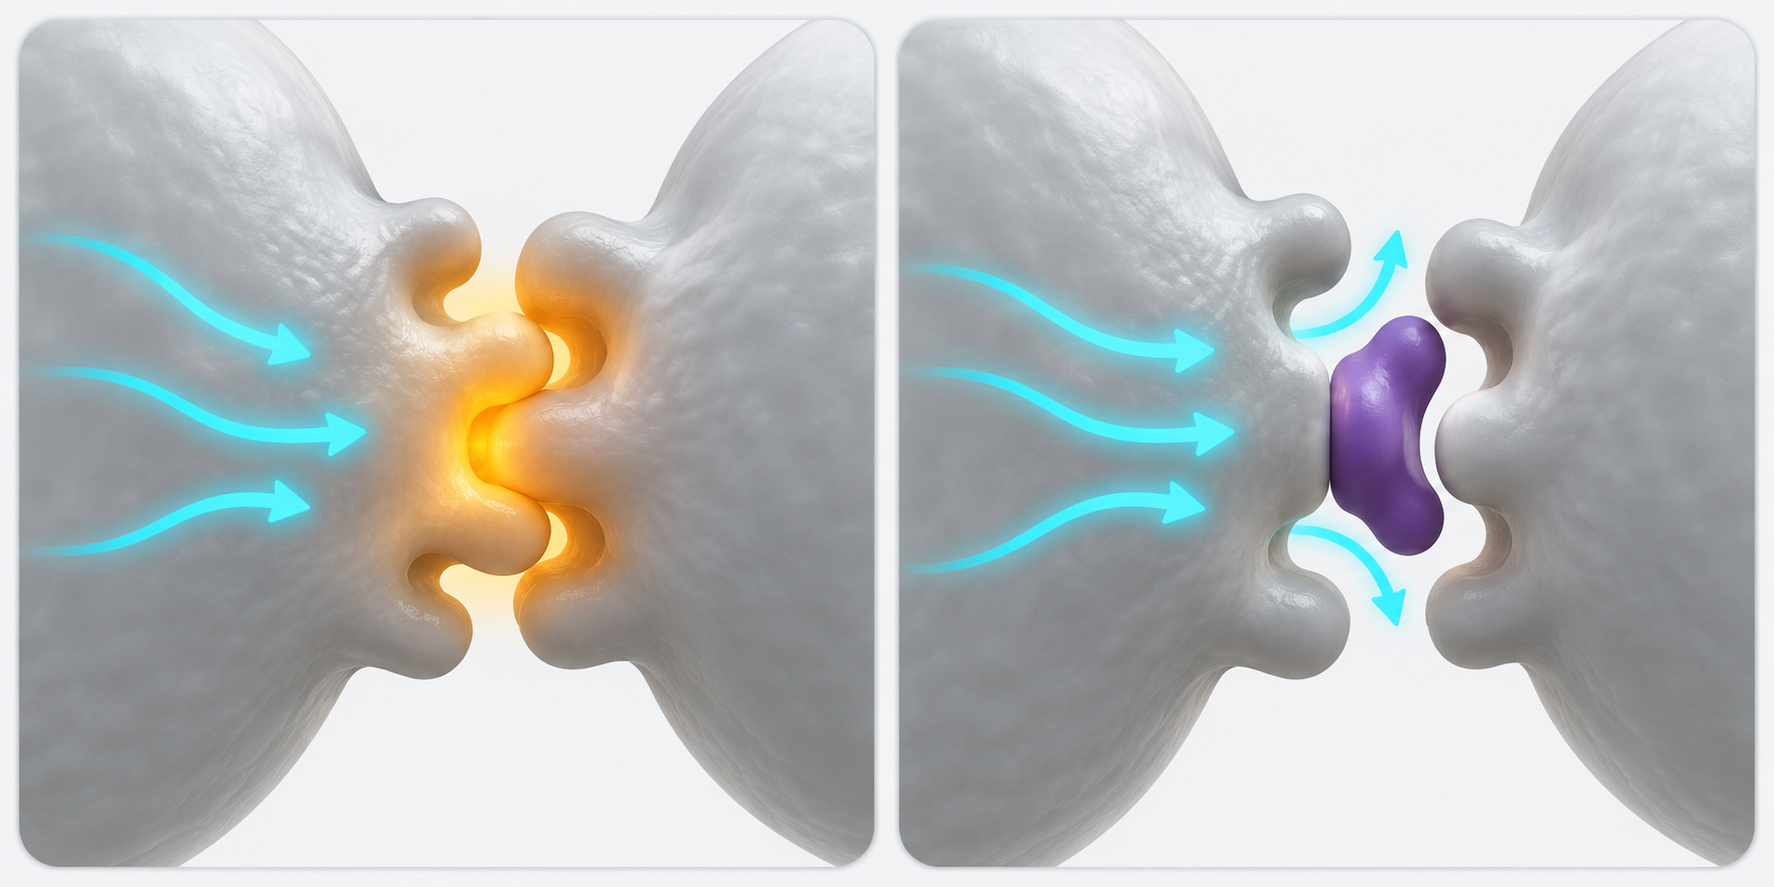
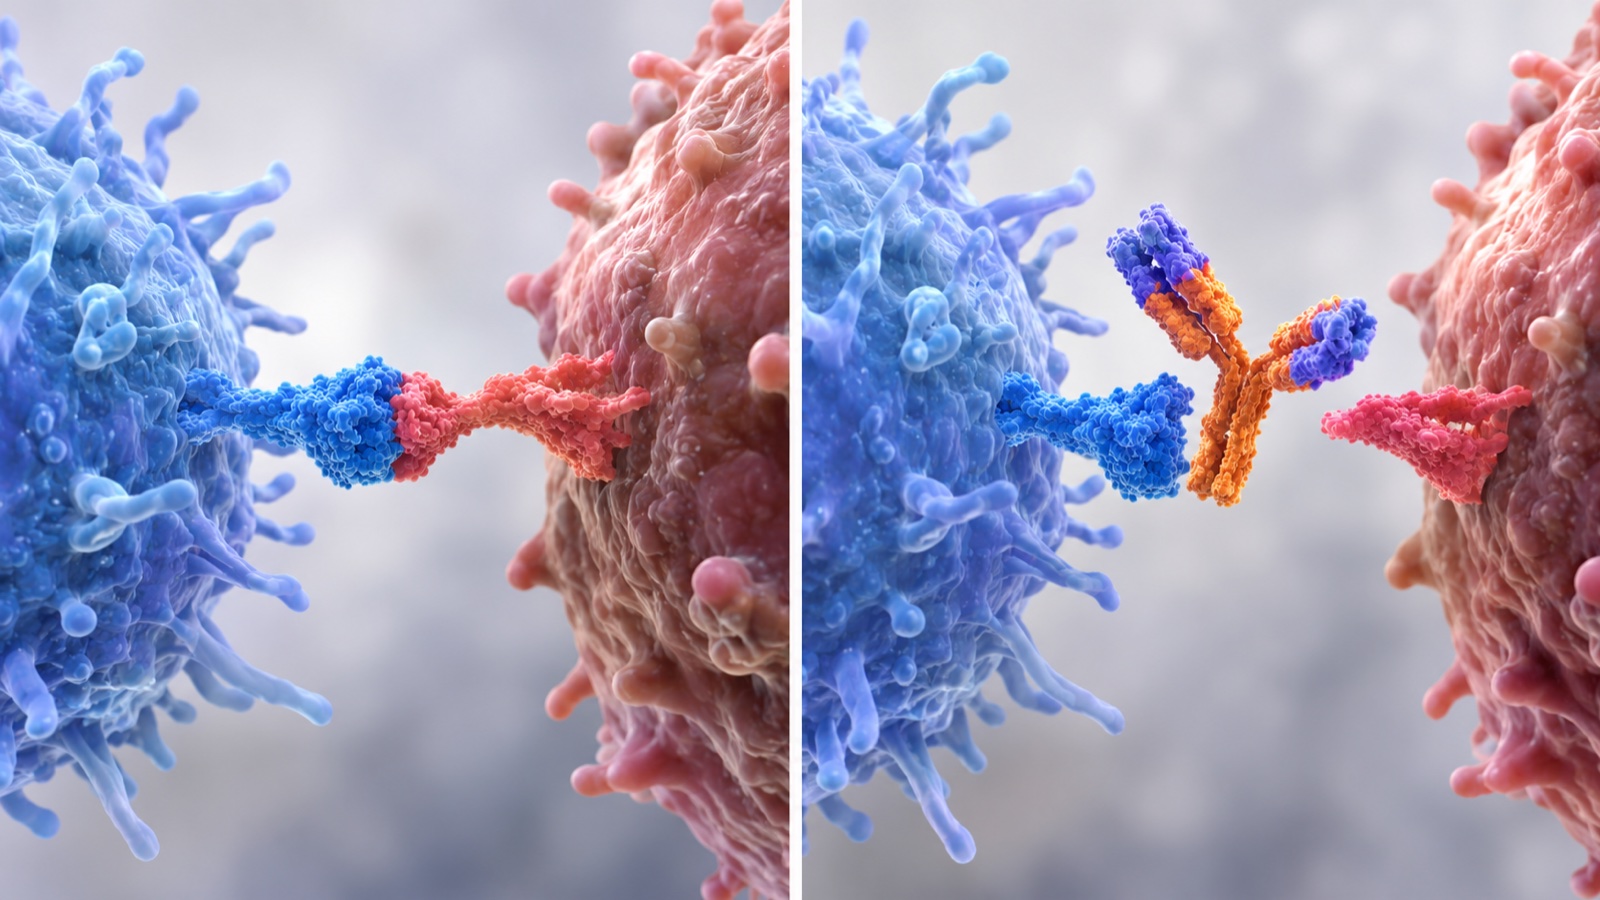
The announcement describes a balance between immune "accelerators and brakes". That balance, it says, is "essential for tight control": it ensures that the immune system attacks foreign microorganisms while "avoiding the excessive activation that can lead to autoimmune destruction of healthy cells and tissues"Sourced
CTLA-4: during the 1990s Allison studied the T-cell protein CTLA-4 at the University of California, Berkeley, and was one of several scientists who observed that CTLA-4 functions as a brake on T cells. He had already developed an antibody that binds CTLA-4 and blocks its function, and he and his co-workers performed a first experiment at the end of 1994Sourced.
PD-1: in 1992, a few years before Allison's discovery, Honjo discovered PD-1, another protein on the surface of T cells. Experiments carried out over many years in his laboratory at Kyoto University showed that PD-1, like CTLA-4, acts as a brake on T cells, but through a different mechanism of actionSourced.
The abstracts of the two original papers can also be checked.
- PD-1 (Ishida et al. 1992, EMBO J): starting from cell lines undergoing programmed cell death, the authors used subtractive hybridization to isolate "the PD-1 gene, a novel member of the immunoglobulin gene superfamily"Sourced. The "PD" in the name comes from this origin (programmed death)
- CTLA-4 (Leach et al. 1996, Science): "in vivo administration of antibodies to CTLA-4 resulted in the rejection of tumors, including preestablished tumors", and the authors conclude that blockade of the inhibitory effects of CTLA-4 "can allow for, and potentiate, effective immune responses against tumor cells"Sourced (these were experiments in mice)
Show the original schematic with sources and figures
Source diagram for Fig. 1 (vector drawing). The description of the brakes and the dates are from the Nobel Foundation [Ref. 1], Ishida et al. [Ref. 2] and Leach et al. [Ref. 3]; the binding partners of the antibodies are from the labels [Refs. 4, 6, 8, 10]. The rectangles are blocks that show roles; they do not show the shape of molecules or cells.
The mechanism-of-action sections of the prescribing information match this figureSourced.
- Ipilimumab: "CTLA-4 is a negative regulator of T-cell activity", and ipilimumab "binds to CTLA-4 and blocks the interaction of CTLA-4 with its ligands, CD80/CD86"
- Nivolumab: "Binding of the PD-1 ligands, PD-L1 and PD-L2, to the PD-1 receptor found on T cells, inhibits T-cell proliferation and cytokine production", and "upregulation of PD-1 ligands occurs in some tumors"
- Atezolizumab: it binds PD-L1 and "blocks its interactions with both PD-1 and B7.1 receptors". The label adds that it activates the anti-tumor immune response "without inducing antibody-dependent cellular cytotoxicity"
The Nobel Foundation announcement also notes that, as with other cancer therapies, adverse side effects are seen, which "can be serious and even life threatening", and that they are caused by an overactive immune response that leads to autoimmune reactionsSourced. The prescribing information for each product likewise carries warnings and precautions about immune-mediated adverse reactionsSourced. This article does not evaluate or discuss the management of side effects.
3. The design of approved antibodies — IgG1, IgG4 and Fc engineering
Even among products that all "inhibit a checkpoint", the antibody's subclass (IgG1 or IgG4) and any modification of the Fc region differ from product to product. The table below lines up what the prescribing information says.
| Product (generic name) | Target | Antibody type (per the label) | Molecular weight | First FDA approval |
|---|---|---|---|---|
| YERVOY (ipilimumab) | CTLA-4 | Recombinant IgG1 kappa immunoglobulin, produced in CHO cell culture | about 148 kDa | 25 March 2011 (BLA 125377) |
| OPDIVO (nivolumab) | PD-1 | IgG4 kappa immunoglobulin (human IgG4), expressed in a recombinant CHO cell line | 146 kDa (calculated) | 22 December 2014 (BLA 125554) |
| KEYTRUDA (pembrolizumab) | PD-1 | Humanized monoclonal IgG4 kappa antibody, produced in recombinant CHO cells | about 149 kDa | 4 September 2014 (BLA 125514) |
| TECENTRIQ (atezolizumab) | PD-L1 | Fc-engineered, humanized, non-glycosylated IgG1 kappa immunoglobulin | 145 kDa (calculated) | 18 May 2016 (BLA 761034) |
Antibody types and molecular weights are from the labels [Refs. 4, 6, 8, 10]; approval dates are from Drugs@FDA [Ref. 12]Sourced. The KEYTRUDA label states that some indications were approved under accelerated approval (an FDA pathway that approves on a surrogate endpoint and requires confirmatory trials)Sourced. BLA = Biologics License Application.
4. A materials engineer's view (1): one residue and one glycan site change an antibody's character
IgG4 has a property that is interesting from a materials-chemistry standpoint. Vidarsson et al. state that the core hinge of IgG4 has the sequence CPSC and that, compared with the relatively rigid CPPC motif of IgG1, "intra-chain disulfide bonds are more easily formed" between the cysteines at positions 226 and 229. As a result, non-covalently linked half-molecules (one heavy chain and one light chain) are observedSourced.
These half-molecules then swap partners. "In vivo, half-molecules of IgG4 recombine randomly with other half-molecules of IgG4, combining specificities of two IgG4 molecules" — this is Fab-arm exchange, which is described as "controlled by redox conditions"Sourced. The review also records that "an S228P mutant of IgG4, thus with an IgG1-core hinge, does not form half-molecules"Sourced.
For nivolumab, the application materials that PMDA published (prepared by Ono Pharmaceutical Co., Ltd., the originator of nivolumab) describe a recombinant human IgG4 monoclonal antibody in which the amino-acid residue at position 221 of the heavy chain is substituted with Pro, and a glycoprotein made up of two heavy chains of 440 amino-acid residues and two light chains of 214 residues (molecular weight about 145,000)Sourced. (Residue numbering differs between sources. We have not confirmed from the material consulted whether "position 221" in the PMDA document and "S228" in Vidarsson et al. refer to the same site.)
In materials terms, this is a design that stops a dynamic covalent exchange reaction by stiffening one spot on the backbone (our commentary). Disulfide exchange is a reaction that self-healing materials and vitrimers use on purpose. In an antibody the aim is the opposite: the exchange is blocked so that the product does not reassemble into different molecules in the body. Of roughly 1,300 residues (440 × 2 + 214 × 2 = 1,308 residuesOur calculation), changing the same single position in each of the two heavy chains is enough to change how the molecule behaves.
The atezolizumab label calls it an "Fc-engineered, humanized, non-glycosylated IgG1", and its mechanism-of-action section says "without inducing antibody-dependent cellular cytotoxicity"Sourced.
In this series' explainer on antibody drugs and ADCs we saw that the presence or absence of a single fucose changes binding to particular Fc receptors greatly. For checkpoint inhibition, the goal is "to block an interaction", not to destroy cells that carry the target. The label states that PD-L1 can be expressed not only on tumor cells but also on tumor-infiltrating immune cellsSourced. So there is an option to design the Fc to switch its activity off rather than add to it. It resembles surface-treatment design, in that on the same antibody scaffold a surface modification may be added or removed depending on the purpose (our commentary).
From a manufacturing standpoint, a design with no glycan removes one control item, glycan heterogeneity (our commentary; the primary sources consulted for this article do not directly describe how glycans are handled in manufacturing control).
5. Biomarkers — letting a test decide who is eligible
In the prescribing information for checkpoint inhibitors, many indications are written with the condition that the tumor be "as determined by an FDA-authorized test". The table picks out three markers used for this purpose in the pembrolizumab labelSourced.
| Marker | What is measured | Example wording in the label |
|---|---|---|
| PD-L1 expression | PD-L1 protein in tumor tissue (immunohistochemistry) | Tumors that express PD-L1 [Combined Positive Score (CPS) ≥1], "as determined by an FDA-authorized test". The descriptions of clinical trials mention determination with the PD-L1 IHC 22C3 pharmDx assay (for example TPS ≥1%) |
| MSI-H / dMMR | Microsatellite instability; deficiency in mismatch repair | "Unresectable or metastatic microsatellite instability-high (MSI-H) or mismatch repair deficient (dMMR) solid tumors, as determined by an FDA-authorized test" |
| TMB-H | Tumor mutational burden | "Unresectable or metastatic tumor mutational burden-high (TMB-H) [≥10 mutations/megabase (mut/Mb)] solid tumors, as determined by an FDA-authorized test" |
All Sourced (KEYTRUDA label [Ref. 6]). Each is an excerpt from part of an indication; they do not give all the conditions a patient must meet. TPS = Tumor Proportion Score; IHC = immunohistochemistry.
PD-L1 status is determined by immunohistochemistry, and the label even names the assay kit (PD-L1 IHC 22C3 pharmDx)Sourced. So, apart from the therapeutic antibody, the antibody reagents that stain the tissue, the color-development system and the standardized procedure are all part of what determines how the product is used. Because eligibility is written as numerical thresholds such as "≥1" and "≥10", the reproducibility of staining and the counting rules can affect the result — the same pattern as in materials test standards, where scatter near a threshold can decide pass or fail. (The primary sources consulted for this article do not describe the composition or manufacture of the assay reagents.)
6. Combinations — CTLA-4 antibodies, and antibody-drug conjugates (ADCs)
Another feature of checkpoint inhibitors is that many indications are for use together with other drugs. From the prescribing information, here are two combinations that stand out from a materials and modality standpoint.
(1) Releasing two brakes at once — a PD-1 antibody plus a CTLA-4 antibody
The mechanism-of-action section of the nivolumab label describes inhibition by nivolumab (anti-PD-1) used together with ipilimumab (anti-CTLA-4) and states that "in murine syngeneic tumor models, dual blockade of PD-1 and CTLA-4 resulted in increased anti-tumor activity"Sourced. This is a combination that releases both of the "two brakes that work through different mechanisms" described in Chapter 2.
(2) Combination with antibody-drug conjugates (ADCs)
The pembrolizumab label lists several indications in which it is combined with an ADCSourced.
- With enfortumab vedotin: "in combination with enfortumab vedotin-ejfv, for the treatment of adult patients with locally advanced or metastatic urothelial cancer". The PADCEV label, in turn, lists use with pembrolizumab, or with pembrolizumab and berahyaluronidase alfa-pmph, as neoadjuvant (before surgery) and then adjuvant (after surgery) treatment of muscle invasive bladder cancerSourced
- With sacituzumab govitecan: "first-line treatment of adult patients with unresectable locally advanced or metastatic TNBC whose tumors express PD-L1 (CPS ≥10) as determined by an FDA-authorized test" (TNBC = triple-negative breast cancer)Sourced
The structure of an ADC (antibody, linker and payload) is covered in more detail in this series' explainer on antibody drugs and ADCs.
This combination can be read as an example of the same antibody scaffold being used for completely opposite purposes (our commentary).
- The antibody in an ADC: a "carrier" that binds the target cell, is taken up into the cell and delivers a cytotoxic drug
- The antibody in a checkpoint inhibitor: a "blocking" material whose purpose is to bind and block an interaction. In some cases, as with atezolizumab, the design deliberately omits the Fc function that destroys cellsSourced
Even among antibodies of the same IgG class, Fc modification, the presence or absence of a glycan, stabilization of the hinge and the presence or absence of an attached drug make them entirely different functional components. An antibody is less a drug than a "platform material" whose surfaces and binding sites are re-engineered for each use (our commentary).
And the fact that the PADCEV label explicitly names use with a subcutaneous product (the berahyaluronidase alfa co-formulation)Sourced shows that the switch in formulation discussed in the next chapter has already reached the way combination regimens are put together (our commentary).
7. Subcutaneous formulations — putting hyaluronidase in the same vial
Between 2024 and 2025 the FDA approved subcutaneous formulations of three checkpoint inhibitorsSourced. Each is a "fixed-dose combination" of an antibody and hyaluronidase (an enzyme that breaks down hyaluronan) in a single vial.
The abstract of a review of the challenges of high-concentration protein formulations says that developing formulations for protein drugs that need high dosing ("in the order of mg/kg") "may become challenging for solubility limited proteins and for the subcutaneous (SC) route with <1.5 mL allowable administration volume that requires >100 mg/mL protein concentrations"Sourced
It calls aggregation, a concentration-dependent degradation route, "the greatest challenge" at these concentrations, and notes that reversible self-association may occur, which "contributes to properties such as viscosity that complicates delivery by injection". Higher viscosity also "complicates manufacturing of high protein concentrations by filtration approaches"Sourced
The label for the subcutaneous nivolumab product (OPDIVO QVANTIG) describes hyaluronidase (human recombinant) as "an endoglycosidase used to increase the dispersion and absorption of co-administered drugs when administered subcutaneously", and as "a glycosylated single-chain protein produced by CHO cells containing a DNA plasmid encoding for a soluble fragment of human hyaluronidase (PH20)" with a molecular weight of approximately 61 kDaSourced.
Its action is temporary. Hyaluronan is "a polysaccharide found in the extracellular matrix of the subcutaneous tissue"; "unlike the stable structural components of the interstitial matrix, hyaluronan has a half-life of approximately 0.5 days", and "hyaluronidase increases permeability of the subcutaneous tissue by temporarily depolymerizing hyaluronan". The label adds that "the effects of hyaluronidase are reversible and permeability of the subcutaneous tissue is restored within 24 to 48 hours"Sourced.
The subcutaneous pembrolizumab product (KEYTRUDA QLEX) uses a different enzyme. Berahyaluronidase alfa is "an endoglycosidase used to enhance dispersion and permeation, which facilitates delivery of increased volume of pembrolizumab" given subcutaneously. It is produced from a variant of human hyaluronidase PH20 and has a molecular weight of about 49 kDa (under nonreducing, deglycosylated conditions)Sourced.
| Formulation | Contents of one vial (per the label) | Excipients | Administration (per the label) |
|---|---|---|---|
| OPDIVO (intravenous) | Nivolumab 10 mg/mL | Mannitol, pentetic acid, polysorbate 80, sodium chloride, sodium citrate; pH 6 | Infused over 30 minutes after dilution |
| OPDIVO QVANTIG (subcutaneous) | Nivolumab 600 mg + hyaluronidase 10,000 units in 5 mL (also 300 mg + 5,000 units in 2.5 mL) | Histidine, histidine hydrochloride, methionine, pentetic acid, polysorbate 80, sucrose; pH 5.5–6.5 | Subcutaneous injection into the abdomen or thigh over 3 to 5 minutes |
| KEYTRUDA (intravenous) | Pembrolizumab 25 mg/mL (100 mg in 4 mL) | L-histidine, polysorbate 80, sucrose 70 mg/mL | Infused over 30 minutes after dilution |
| KEYTRUDA QLEX (subcutaneous) | Pembrolizumab 395 mg + berahyaluronidase alfa 4,800 units in 2.4 mL (also 790 mg + 9,600 units in 4.8 mL) | Histidine, histidine hydrochloride, methionine, polysorbate 80, sucrose; pH 5.3–5.9 | 2.4 mL injected subcutaneously over 1 minute; 4.8 mL over 2 minutes |
| TECENTRIQ (intravenous) | Atezolizumab 1,200 mg in 20 mL (also 840 mg in 14 mL) | Glacial acetic acid, L-histidine, polysorbate 20, sucrose; pH 5.8 | First infusion over 60 minutes; later infusions over 30 minutes if tolerated |
| TECENTRIQ HYBREZA (subcutaneous) | Atezolizumab 1,875 mg + hyaluronidase 30,000 units in 15 mL | Histidine, methionine, polysorbate 20, sucrose 1,232 mg; pH 5.8 adjusted with acetic acid | Subcutaneous injection into the thigh over about 7 minutes |
All Sourced (labels [Refs. 4–9]). All three subcutaneous products are labelled for storage at 2–8 °C, avoiding freezing and shakingSourced. Administration times are quoted to explain formulation design; they are not a recommendation of one route over the other.
8. Our calculation: how many times more concentrated, and how many mL per minute?
The values below are converted from the figures in the tableOur calculation.
- Antibody concentration: nivolumab 600 ÷ 5 = 120 mg/mL (12 times the 10 mg/mL of the intravenous product); pembrolizumab 395 ÷ 2.4 = about 165 mg/mL (about 6.6 times the 25 mg/mL); atezolizumab 1,875 ÷ 15 = 125 mg/mL (about 2.1 times the 1,200 ÷ 20 = 60 mg/mL)
- Relation to Shire et al.'s rule of thumb: all three reach concentrations "above 100 mg/mL". The injected volume, however, is 2.4–15 mL, which is about 1.6 to 10 times the "<1.5 mL" figure
- Injection speed: atezolizumab 15 mL ÷ about 7 min = about 2.1 mL/min; pembrolizumab 2.4 mL ÷ 1 min = 4.8 mL ÷ 2 min = 2.4 mL/min; nivolumab 5 mL ÷ 3–5 min = 1.0–1.7 mL/min
- Enzyme concentration: nivolumab 10,000 units ÷ 5 mL, pembrolizumab 4,800 units ÷ 2.4 mL, atezolizumab 30,000 units ÷ 15 mL — exactly 2,000 units/mL for all three
- Sugar (sucrose) concentration: subcutaneous pembrolizumab 168 mg ÷ 2.4 mL = 70 mg/mL (the same as the intravenous product); subcutaneous atezolizumab 1,232 ÷ 15 = about 82 mg/mL
Assumptions and limits: each concentration is the labelled amount in the vial divided by its volume. Shire et al.'s "<1.5 mL" is a general rule of thumb from a 2004 review, not a design criterion for any individual product. That the three enzyme concentrations are identical is a coincidence in the arithmetic; the reason is not given in the material consulted for this article. These figures are for looking at how the formulations are put together; they do not show efficacy, safety, or the superiority of any route of administration.
9. A materials engineer's view (2): a high-concentration protein and an enzyme in one vial

Re-reading the label's explanation in materials language, the mechanism of the subcutaneous products is temporary breakdown of a gel network (our commentary).
- Hyaluronan is "a polysaccharide found in the extracellular matrix of the subcutaneous tissue" and has a half-life of about 0.5 days, a fast turnover for a structural componentSourced
- Hyaluronidase "temporarily depolymerizes" it to raise permeability, and the effect is restored within 24 to 48 hoursSourced
In other words, the molecular weight of the polymer network is lowered locally so that fluid can flow more easily. Rather than only changing the liquid that is injected (which can be highly concentrated and highly viscous), the resistance of the receiving medium is lowered as well — an approach to pushing a fluid into a porous body that modifies both the fluid side and the medium side (our commentary). It is because this network naturally turns over quickly that "breaking it temporarily, and having it return" works.
The container of a subcutaneous product holds an antibody of about 145–149 kDa together with an enzyme of about 49–61 kDaSourced. The antibody is at the high concentration of 120–165 mg/mLOur calculation, while the enzyme is labelled in units (activity)Sourced.
As Shire et al. point out, at high concentration aggregation is the greatest challenge, and reversible self-association raises viscosity and makes manufacturing by filtration harderSourced. Inside that same liquid, the other protein (the enzyme) has to keep its activity. What is required is a formulation that is both "concentrated without aggregating" and "mixed without damaging each other" (our commentary).
Comparing the lists of excipients shows one patternSourced.
- All three subcutaneous products contain histidine, methionine, polysorbate and sucrose
- The excipients listed in the labels of the intravenous OPDIVO, KEYTRUDA and TECENTRIQ do not include methionine
Because the labels do not state the purpose of each excipient, this article does not assert why methionine was added. Still, the fact that a component was added in common when the formulation was made more concentrated and shared with an enzyme is worth reading as a clue to formulation design (our commentary).
One more point: in the calculation in Chapter 8, the enzyme concentration was the same, 2,000 units/mL, for all three productsOur calculation. Although the three products from three companies differ in antibody and in enzyme (two use a soluble fragment of PH20, one a variant of it), the amount of enzyme per unit volume is the same. The material consulted does not give a reason, but we record the match as a coincidence that suggests the enzyme part of the formulation may be a "common recipe value" that does not depend on the antibody (our commentary).
10. Approval status (as confirmed from regulators' published materials)
| Product (generic name) | Dosage form | First FDA approval | Notes |
|---|---|---|---|
| YERVOY (ipilimumab) | Intravenous infusion | 25 March 2011 (BLA 125377) | Antibody against CTLA-4 |
| KEYTRUDA (pembrolizumab) | Intravenous infusion | 4 September 2014 (BLA 125514) | The label states that some indications are based on accelerated approval |
| OPDIVO (nivolumab) | Intravenous infusion | 22 December 2014 (BLA 125554) | According to the application materials published by PMDA (prepared by Ono Pharmaceutical), it was approved in Japan in July 2014 as "OPDIVO for Intravenous Infusion 20 mg and 100 mg", and received accelerated approval in the US in December 2014 |
| TECENTRIQ (atezolizumab) | Intravenous infusion | 18 May 2016 (BLA 761034) | Fc-engineered, non-glycosylated IgG1 |
| TECENTRIQ HYBREZA | Subcutaneous injection (with hyaluronidase) | 12 September 2024 (BLA 761347, standard review) | Atezolizumab + hyaluronidase-tqjs |
| OPDIVO QVANTIG | Subcutaneous injection (with hyaluronidase) | 27 December 2024 (BLA 761381 and another, standard review) | Nivolumab + hyaluronidase-nvhy |
| KEYTRUDA QLEX | Subcutaneous injection (with berahyaluronidase alfa) | 19 September 2025 (BLA 761467, priority review) | Pembrolizumab + berahyaluronidase alfa-pmph |
Approval dates and review classes are from FDA Drugs@FDA [Ref. 12]; dosage forms and accelerated-approval statements are from the labels [Refs. 4–10]; the timing of approval in Japan is from the PMDA materials [Ref. 15]Sourced. Drugs@FDA lists two BLAs for OPDIVO QVANTIG, 761381 and 761429, as approved on the same day. The status of the three subcutaneous products in Japan (PMDA) was not confirmed as of the research for this article (September 2026)Not yet confirmed.
- Checkpoint inhibitors use antibodies to block binding to the T-cell brakes (CTLA-4, PD-1) and to their partner (PD-L1)Sourced
- The antibody type differs by product. There are IgG1, IgG4 and Fc-engineered, non-glycosylated IgG1, and nivolumab has one hinge residue substituted with ProSourced
- Half-molecule formation and Fab-arm exchange in IgG4 are a chemical phenomenon, the swapping of disulfide bondsSourced
- Many indications are written together with an "FDA-authorized test". There are three yardsticks: PD-L1, MSI-H/dMMR and TMB-HSourced
- In the subcutaneous products the antibody is about 2.1 to 12 times as concentrated as in the intravenous ones, and the enzyme concentration is 2,000 units/mL in all threeOur calculation
- Hyaluronidase temporarily depolymerizes hyaluronan in subcutaneous tissue, and permeability returns within 24 to 48 hoursSourced
11. Glossary
- Immune checkpoint
- A braking mechanism that prevents excessive activation of the immune system, such as CTLA-4 and PD-1.
- CTLA-4
- A negative regulator of T-cell activity. It binds CD80/CD86.
- PD-1
- A receptor on T cells. Binding of PD-L1 or PD-L2 suppresses proliferation.
- PD-L1
- The partner of PD-1. It can be expressed on tumor cells and on immune cells that infiltrate a tumor.
- IgG1 / IgG4
- Antibody subclasses. The hinge and Fc differ in their properties.
- Hinge
- The region joining the Fab arms to the Fc of an antibody. It contains the inter-chain disulfide bonds.
- Fab-arm exchange
- The phenomenon in which a half-molecule of IgG4 recombines with a half-molecule of another IgG4.
- Fc engineering
- Changing amino acids or glycans in the Fc to tune how strongly immune cells are recruited.
- Antibody-dependent cellular cytotoxicity (ADCC)
- The process in which immune cells damage a target cell through the Fc of an antibody.
- CPS / TPS
- Scores for the positivity of PD-L1 staining (Combined Positive Score, Tumor Proportion Score). Used as decision thresholds.
- MSI-H / dMMR
- High microsatellite instability / deficiency in mismatch repair.
- TMB-H
- High tumor mutational burden, expressed as mutations per megabase.
- Hyaluronan
- Hyaluronic acid. A polysaccharide in the extracellular matrix of subcutaneous tissue.
- Hyaluronidase
- An enzyme that breaks down hyaluronan. In subcutaneous products it increases dispersion and absorption.
- PH20
- A human hyaluronidase. The products use a soluble fragment or a variant of it.
- Fixed-dose combination
- A product that combines several active ingredients in one formulation in a set ratio.
- Self-association
- Reversible clustering of protein molecules. One cause of rising viscosity.
- Accelerated approval
- An FDA pathway that approves a drug on a surrogate endpoint and requires confirmatory trials to verify it.
12. References (primary sources)
- The Nobel Assembly at Karolinska Institutet "The Nobel Prize in Physiology or Medicine 2018 — Press release", 1 October 2018 — nobelprize.org
- Ishida, Y., Agata, Y., Shibahara, K., Honjo, T. "Induced expression of PD-1, a novel member of the immunoglobulin gene superfamily, upon programmed cell death", The EMBO Journal 11(11), 3887–3895 (1992). doi:10.1002/j.1460-2075.1992.tb05481.x — pmc.ncbi.nlm.nih.gov
- Leach, D.R., Krummel, M.F., Allison, J.P. "Enhancement of antitumor immunity by CTLA-4 blockade", Science 271(5256), 1734–1736 (1996). doi:10.1126/science.271.5256.1734 — pubmed.ncbi.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "OPDIVO (nivolumab) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "OPDIVO QVANTIG (nivolumab and hyaluronidase-nvhy) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "KEYTRUDA (pembrolizumab) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "KEYTRUDA QLEX (pembrolizumab and berahyaluronidase alfa-pmph) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "TECENTRIQ (atezolizumab) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "TECENTRIQ HYBREZA (atezolizumab and hyaluronidase-tqjs) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "YERVOY (ipilimumab) injection" — dailymed.nlm.nih.gov
- DailyMed (FDA-approved prescribing information) "PADCEV (enfortumab vedotin-ejfv)" — dailymed.nlm.nih.gov
- FDA "Drugs@FDA: FDA-Approved Drugs" (first approval date and review class for each BLA) — accessdata.fda.gov
- Vidarsson, G., Dekkers, G., Rispens, T. "IgG subclasses and allotypes: from structure to effector functions", Frontiers in Immunology 5, 520 (2014). doi:10.3389/fimmu.2014.00520 — pmc.ncbi.nlm.nih.gov
- Shire, S.J., Shahrokh, Z., Liu, J. "Challenges in the development of high protein concentration formulations", Journal of Pharmaceutical Sciences 93(6), 1390–1402 (2004). doi:10.1002/jps.20079 — pubmed.ncbi.nlm.nih.gov
- Pharmaceuticals and Medical Devices Agency (PMDA), published materials (prepared by Ono Pharmaceutical Co., Ltd.) "Materials concerning OPDIVO Intravenous Infusion 20 mg and OPDIVO Intravenous Infusion 100 mg" (in Japanese), 2016 (PDF) — pmda.go.jp
13. Claim-to-source audit
| Claim in the text | Basis | Class |
|---|---|---|
| That the 2018 Nobel Prize in Physiology or Medicine was awarded to Allison and Honjo for the discovery of cancer therapy by inhibition of negative immune regulation, and that the announcement date was 1 October 2018. That the two showed that strategies for inhibiting the brakes on the immune system can be used to treat cancer. That the balance between accelerators and brakes is essential for avoiding autoimmune destruction. That Allison studied CTLA-4 at the University of California, Berkeley in the 1990s, was one of those who observed it to act as a brake on T cells, had developed an antibody that blocks CTLA-4, and performed a first experiment at the end of 1994. That Honjo discovered PD-1 in 1992 and that his work at Kyoto University showed PD-1 to act as a brake like CTLA-4 through a different mechanism. That side effects can be serious and even life threatening and are caused by an overactive immune response leading to autoimmune reactions | Nobel Foundation press release, Nobel Prize in Physiology or Medicine 2018 Reference 1 https://www.nobelprize.org/prizes/medicine/2018/press-release/ | Sourced |
| That the PD-1 gene, a novel member of the immunoglobulin gene superfamily, was isolated by subtractive hybridization from cell lines undergoing programmed cell death | Abstract of Ishida et al. (1992) Reference 2 https://pmc.ncbi.nlm.nih.gov/articles/PMC556898/ | Sourced |
| That in vivo administration of antibodies to CTLA-4 resulted in rejection of tumors, including preestablished tumors, and the conclusion that blockade of the inhibitory effects of CTLA-4 can allow for and potentiate effective immune responses against tumor cells (experiments in mice) | Abstract of Leach et al. (1996) Reference 3 https://pubmed.ncbi.nlm.nih.gov/8596936/ | Sourced |
| That nivolumab is a PD-1-blocking IgG4 kappa immunoglobulin (human IgG4) with a calculated molecular mass of 146 kDa, expressed in a recombinant CHO cell line. That OPDIVO is 10 mg/mL, contains mannitol, pentetic acid, polysorbate 80, sodium chloride and sodium citrate at pH 6, and is infused over 30 minutes after dilution. That binding of PD-L1 and PD-L2 to PD-1 inhibits T-cell proliferation and cytokine production and that upregulation of PD-1 ligands occurs in some tumors. The description of inhibition by nivolumab together with ipilimumab, and that dual blockade of PD-1 and CTLA-4 increased anti-tumor activity in murine syngeneic tumor models | OPDIVO prescribing information Reference 4 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=f570b9c4-6846-4de2-abfa-4d0a4ae4e394 | Sourced |
| That OPDIVO QVANTIG is a fixed-dose combination of nivolumab and hyaluronidase (human recombinant). That the hyaluronidase is an endoglycosidase that increases dispersion and absorption of co-administered drugs when given subcutaneously, a glycosylated single-chain protein produced by CHO cells containing a plasmid encoding a soluble fragment of human PH20, with a molecular weight of about 61 kDa. 600 mg + 10,000 units in 5 mL and 300 mg + 5,000 units in 2.5 mL; excipients (histidine, histidine hydrochloride, methionine, pentetic acid, polysorbate 80, sucrose); pH 5.5–6.5. Subcutaneous injection into the abdomen or thigh over 3 to 5 minutes; storage at 2–8 °C, avoiding freezing and shaking. That hyaluronan is a polysaccharide of the extracellular matrix of subcutaneous tissue with a half-life of about 0.5 days, that hyaluronidase temporarily depolymerizes it to raise permeability, and that the effect is reversible with permeability restored within 24 to 48 hours | OPDIVO QVANTIG prescribing information Reference 5 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=7f8c38fa-42f4-4387-9e8c-7a1c66855d8b | Sourced |
| That pembrolizumab is a humanized monoclonal IgG4 kappa antibody of about 149 kDa produced in recombinant CHO cells. That KEYTRUDA is 100 mg in 4 mL (25 mg/mL), contains L-histidine, polysorbate 80 and sucrose 70 mg/mL, and is infused over 30 minutes after dilution. That some indications are based on accelerated approval. The indications that specify determination by an FDA-authorized test for PD-L1 (CPS ≥1), MSI-H/dMMR solid tumors and TMB-H (≥10 mutations/megabase) solid tumors, and that clinical trials used determination with PD-L1 IHC 22C3 pharmDx (for example TPS ≥1%). The indication for locally advanced or metastatic urothelial cancer in combination with enfortumab vedotin, and the first-line indication for PD-L1 (CPS ≥10) triple-negative breast cancer in combination with sacituzumab govitecan | KEYTRUDA prescribing information Reference 6 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=9333c79b-d487-4538-a9f0-71b91a02b287 | Sourced |
| That KEYTRUDA QLEX is a fixed-dose combination of pembrolizumab and berahyaluronidase alfa; that berahyaluronidase alfa is an endoglycosidase, a variant of human hyaluronidase PH20, that enhances dispersion and permeation and so allows an increased volume of pembrolizumab, with a molecular weight of about 49 kDa (nonreducing, deglycosylated conditions). 395 mg + 4,800 units in 2.4 mL and 790 mg + 9,600 units in 4.8 mL; excipients (histidine, histidine hydrochloride, methionine, polysorbate 80, sucrose 168 mg in 2.4 mL); pH 5.3–5.9. Subcutaneous injection of 2.4 mL over 1 minute and 4.8 mL over 2 minutes. Storage at 2–8 °C, avoiding freezing and shaking, and that the effect is reversible with permeability restored within 24 to 48 hours | KEYTRUDA QLEX prescribing information Reference 7 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=097d166f-b73b-41d3-9b37-7653cd2a0c41 | Sourced |
| That atezolizumab is a PD-L1-blocking Fc-engineered, humanized, non-glycosylated IgG1 kappa immunoglobulin with a calculated molecular mass of 145 kDa. That TECENTRIQ is 1,200 mg in 20 mL and 840 mg in 14 mL, contains glacial acetic acid, L-histidine, polysorbate 20 and sucrose at pH 5.8, and is infused over 60 minutes for the first infusion and over 30 minutes thereafter if tolerated. That PD-L1 can be expressed on tumor cells and tumor-infiltrating immune cells, and that atezolizumab binds PD-L1, blocks its interactions with PD-1 and B7.1 and activates the anti-tumor immune response without inducing antibody-dependent cellular cytotoxicity | TECENTRIQ prescribing information Reference 8 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=6fa682c9-a312-4932-9831-f286908660ee | Sourced |
| That TECENTRIQ HYBREZA is a fixed-dose combination of atezolizumab and hyaluronidase (human recombinant, a soluble fragment of PH20, about 61 kDa); 1,875 mg + 30,000 units in 15 mL; excipients (histidine 46.5 mg, methionine 22.4 mg, polysorbate 20 9 mg, sucrose 1,232 mg); pH 5.8 with acetic acid; subcutaneous injection into the thigh over about 7 minutes; storage at 2–8 °C, avoiding freezing and shaking; and that the effect of hyaluronidase is reversible with permeability restored within 24 to 48 hours | TECENTRIQ HYBREZA prescribing information Reference 9 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a617b089-ce66-464b-987b-b45d029b4d6f | Sourced |
| That ipilimumab is a CTLA-4-blocking recombinant IgG1 kappa immunoglobulin of about 148 kDa produced in CHO cell culture. That CTLA-4 is a negative regulator of T-cell activity and that ipilimumab binds CTLA-4 and blocks its interaction with CD80/CD86 | YERVOY prescribing information Reference 10 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=2265ef30-253e-11df-8a39-0800200c9a66 | Sourced |
| That enfortumab vedotin is indicated, in combination with pembrolizumab or with pembrolizumab and berahyaluronidase alfa, as neoadjuvant and adjuvant treatment of muscle invasive bladder cancer | PADCEV prescribing information Reference 11 https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=b5631d3e-4604-4363-8f20-11dfc5a4a8ed | Sourced |
| First FDA approval dates and review classes (YERVOY 25 March 2011 / BLA 125377; KEYTRUDA 4 September 2014 / BLA 125514; OPDIVO 22 December 2014 / BLA 125554; TECENTRIQ 18 May 2016 / BLA 761034; TECENTRIQ HYBREZA 12 September 2024 / BLA 761347, standard review; OPDIVO QVANTIG 27 December 2024 / BLAs 761381 and 761429, standard review; KEYTRUDA QLEX 19 September 2025 / BLA 761467, priority review) | FDA Drugs@FDA summaries for each BLA Reference 12 https://www.accessdata.fda.gov/scripts/cder/daf/index.cfm | Sourced |
| That the core hinge of IgG4 is CPSC, that intra-chain disulfide bonds form more easily between the cysteines at positions 226 and 229 than in the CPPC hinge of IgG1, and that non-covalently linked half-molecules (one heavy and one light chain) are observed. That the S228P mutant, with an IgG1-type core hinge, does not form half-molecules. That in vivo half-molecules of IgG4 recombine randomly with other IgG4 half-molecules (Fab-arm exchange), controlled by redox conditions | Vidarsson et al. (2014) Reference 13 https://pmc.ncbi.nlm.nih.gov/articles/PMC4202688/ | Sourced |
| That developing formulations for protein drugs needing high dosing becomes difficult for the subcutaneous route, with an allowable volume under 1.5 mL and a required concentration above 100 mg/mL; that concentration-dependent aggregation is the greatest challenge; and that reversible self-association contributes to viscosity, which complicates injection, and higher viscosity complicates manufacturing by filtration | Abstract of Shire et al. (2004) Reference 14 https://pubmed.ncbi.nlm.nih.gov/15124199/ | Sourced |
| That nivolumab is a recombinant human IgG4 monoclonal antibody whose heavy-chain residue 221 is substituted with Pro, a glycoprotein of two 440-residue heavy chains and two 214-residue light chains (molecular weight about 145,000) produced in CHO cells. That it was approved in Japan in July 2014 as "OPDIVO for Intravenous Infusion 20 mg and 100 mg" for unresectable malignant melanoma, and received accelerated approval in the US in December 2014 (per materials prepared by Ono Pharmaceutical and published by PMDA) | PMDA published materials (OPDIVO for Intravenous Infusion, prepared by Ono Pharmaceutical) Reference 15 https://www.pmda.go.jp/drugs/2016/P20161208002/180188000_22600AMX00768_B100_1.pdf | Sourced |
| That the subcutaneous antibody concentrations are 120 mg/mL (12 times), about 165 mg/mL (about 6.6 times) and 125 mg/mL (about 2.1 times). That the 2.4–15 mL volumes are about 1.6 to 10 times the "<1.5 mL" figure. That the injection rates are about 2.1 mL/min, 2.4 mL/min and 1.0–1.7 mL/min. That the enzyme concentration is 2,000 units/mL for all three. That the sucrose concentrations are 70 mg/mL and about 82 mg/mL. That the heavy and light chain residue counts give about 1,308 residues | Our calculation. Each concentration is the labelled amount in the vial divided by its volume; Shire et al.'s guide is a general statement, not a design criterion for any individual product. It does not show efficacy, safety or the superiority of any route of administration. | Our calculation |
| The status of the three subcutaneous products in Japan (PMDA) | Not confirmed as of the research for this article (September 2026) | Not yet confirmed |
| The purpose of each excipient such as methionine, the reason the three enzyme concentrations match, whether "position 221" and "S228" are the same site, the effect of a non-glycosylated design on manufacturing control, and the composition of assay reagents | Not described in the primary sources consulted for this article and so could not be confirmed; not asserted | Commentary |
| The relative merits of each product's indications, clinical results, safety assessment, and infusion versus subcutaneous injection | This article explains antibody design and formulation technology and does not evaluate efficacy or safety. Administration times and concentrations are quoted from the labels to explain formulation design | Commentary |
| The reading of the IgG4 hinge substitution as "a design that stops dynamic covalent exchange by stiffening the backbone". The reading of non-glycosylation as a design that switches off Fc activity, likened to surface treatment. The split into "carrier" and "blocking" antibodies and the reading of the antibody as a "platform material". The framing of subcutaneous tissue as a hydrogel and of hyaluronidase as temporarily loosening its network. The reading of the co-existence of a high-concentration antibody and an enzyme as a formulation-design problem. The reading of the excipients common to the subcutaneous products. The likening of assay thresholds and reproducibility to materials testing | This article's own organization and commentary based on published content; not views expressed by the authors of the papers, regulators or companies | Commentary |
| That the figures combine ImageGen-generated explanatory images with vector drawings, and are distinguished from real objects or measured images | Note by this article | Commentary |
Last updated 26 September 2026. Sources are limited to primary material (the Nobel Foundation announcement, FDA-approved prescribing information and Drugs@FDA, PMDA published materials, and peer-reviewed papers). Because the article includes readings of antibody design and formulation design, those are marked as Commentary and kept separate from sourced fact. The purposes of the excipients, the reason the enzyme concentrations match, and the status of the subcutaneous products in Japan could not be confirmed from the primary information published, and are not stated here. The structure and manufacture of antibodies in general are covered in this series' explainer on antibody drugs and ADCs. This article explains antibody design and formulation technology; it does not evaluate the efficacy or safety of any treatment and is not medical advice. All figures are explanatory concept graphics. The figures combine ImageGen-generated explanatory images with vector drawings. The generated images are not photographs of real objects, micrographs or measured data. The original schematics, which contain figures and sources, are kept either as displayed or in a form that can be expanded below the new images.